İHALE DÜNYASI
İHALE DÜNYASI
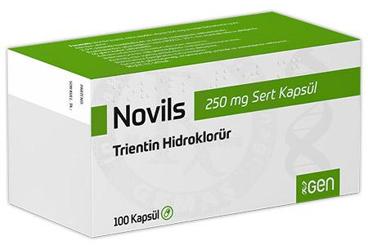
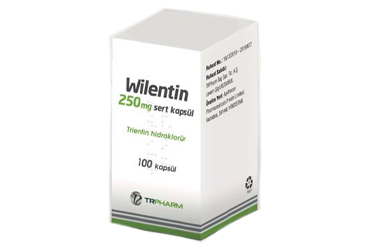
Trientine hydrochloride, USP is N,N' -bis (2-aminoethyl)-1,2-ethanediamine dihydrochloride. It is a white to pale yellow crystalline hygroscopic powder. It is freely soluble in water, soluble in methanol, slightly soluble in ethanol, and insoluble in chloroform and ether. The molecular formula is C 6 H 18 N 4 *2HCl with a molecular weight of 219.2. The structural formula is: NH 2 (CH 2 ) 2 NH(CH 2 ) 2 NH(CH 2 ) 2 NH 2 *2HCl Trientine hydrochloride, USP is a chelating compound for removal of excess copper from the body. Trientine hydrochloride, USP is available as 250 mg and 500 mg capsules for oral administration. Trientine hydrochloride capsules, USP contain gelatin, iron oxide black, iron oxide red, iron oxide yellow, potassium hydroxide, propylene glycol, shellac, stearic acid and titanium dioxide as inactive ingredients.
Trientine hydrochloride is indicated in the treatment of patients with Wilson's disease who are intolerant of penicillamine. Clinical experience with trientine hydrochloride is limited and alternate dosing regimens have not been well-characterized; all endpoints in determining an individual patient's dose have not been well defined. Trientine hydrochloride and penicillamine cannot be considered interchangeable. Trientine hydrochloride should be used when continued treatment with penicillamine is no longer possible because of intolerable or life endangering side effects. Unlike penicillamine, trientine hydrochloride is not recommended in cystinuria or rheumatoid arthritis. The absence of a sulfhydryl moiety renders it incapable of binding cystine and, therefore, it is of no use in cystinuria. In 15 patients with rheumatoid arthritis, trientine hydrochloride was reported not to be effective in improving any clinical or biochemical parameter after 12 weeks of treatment. Trientine hydrochloride is not indicated for treatment of biliary cirrhosis.
Hypersensitivity to this product.
Clinical experience with trientine hydrochloride has been limited. The following adverse reactions have been reported in a clinical study in patients with Wilson's disease who were on therapy with trientine hydrochloride: iron deficiency, systemic lupus erythematosus (see CLINICAL PHARMACOLOGY ). In addition, the following adverse reactions have been reported in marketed use: dystonia, muscular spasm, myasthenia gravis. Trientine hydrochloride is not indicated for treatment of biliary cirrhosis, but in one study of 4 patients treated with trientine hydrochloride for primary biliary cirrhosis, the following adverse reactions were reported: heartburn; epigastric pain and tenderness; thickening, fissuring and flaking of the skin; hypochromic microcytic anemia; acute gastritis; aphthoid ulcers; abdominal pain; melena; anorexia; malaise; cramps; muscle pain; weakness; rhabdomyolysis. A causal relationship of these reactions to drug therapy could not be rejected or established. To report SUSPECTED ADVERSE EVENTS, contact Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or http://www.fda.gov/ for voluntary reporting of adverse reactions.
Patient experience with trientine hydrochloride is limited (see CLINICAL PHARMACOLOGY ). Patients receiving trientine hydrochloride capsules should remain under regular medical supervision throughout the period of drug administration. Patients (especially women) should be closely monitored for evidence of iron deficiency anemia.
In general, mineral supplements should not be given since they may block the absorption of trientine hydrochloride. However, iron deficiency may develop, especially in children and menstruating or pregnant women, or as a result of the low copper diet recommended for Wilson's disease. If necessary, iron may be given in short courses, but since iron and trientine hydrochloride each inhibit absorption of the other, two hours should elapse between administration of trientine hydrochloride capsules and iron. It is important that trientine hydrochloride capsules be taken on an empty stomach, at least one hour before meals or two hours after meals and at least one hour apart from any other drug, food, or milk. This permits maximum absorption and reduces the likelihood of inactivation of the drug by metal binding in the gastrointestinal tract.