

İHALE DÜNYASI
İHALE DÜNYASI
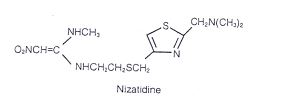
Nizatidine, USP is a histamine H 2 -receptor antagonist. Chemically, it is N-[2-[[[2- [(dimethylamino)methyl]-4-thiazolyl]methyl]thio]ethyl]-N ' -methyl-2-nitro-1,1-ethenediamine. The structural formula is as follows: Nizatidine USP has the empirical formula C 12 H 21 N 5 O 2 S 2 representing a molecular weight of 331.46. It is an off-white to buff crystalline solid that is sparingly soluble in water. Nizatidine USP has a bitter taste and mild sulfur-like odor. Each nizatidine capsule USP contains for oral administration corn starch, magnesium stearate, povidone, pregelatinized starch, sodium starch glycolate and 150 mg (0.45 mmol) or 300 mg (0.91 mmol) of nizatidine USP. The 150 mg capsule shell contains ferric oxide yellow, titanium dioxide, sodium lauryl sulphate and gelatin .The 300 mg capsule shell contains FD&C Blue 1, FD&C Red 40, D&C Yellow 10, FD&C Yellow 6, titanium dioxide, sodium lauryl sulphate and gelatin.The imprinting ink for capsule shell contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, strong ammonia solution, black iron oxide, pottasium hydroxide and purified water. structure
Nizatidine capsules USP are indicated for up to 8 weeks for the treatment of active duodenal ulcer. In most patients, the ulcer will heal within 4 weeks. Nizatidine capsules USP are indicated for maintenance therapy for duodenal ulcer patients at a reduced dosage of 150 mg h.s. after healing of an active duodenal ulcer. The consequences of continuous therapy with nizatidine for longer than 1 year are not known. Nizatidine capsules USP are indicated for up to 12 weeks for the treatment of endoscopically diagnosed esophagitis, including erosive and ulcerative esophagitis, and associated heartburn due to GERD. Nizatidine capsules USP are indicated for up to 8 weeks for the treatment of active benign gastric ulcer. Before initiating therapy, care should be taken to exclude the possibility of malignant gastric ulceration.
Active Duodenal Ulcer The recommended oral dosage of adults is 300 mg once daily at bedtime. An alternative dosage regimen is 150 mg twice daily. Maintenance of Healed Duodenal Ulcer The recommended oral dosage for adults is 150 mg once daily at bedtime. Gastroesophageal Reflux Disease The recommended oral dosage in adults for the treatment of erosions, ulcerations, and associated heartburn is 150 mg twice daily. Active Benign Gastric Ulcer The recommended oral dosage is 300 mg given either as 150 mg twice daily or 300 mg once daily at bedtime. Prior to treatment, care should be taken to exclude the possibility of malignant gastric ulceration. Dosage Adjustment for Patients With Moderate to Severe Renal Insufficiency The dose for patients with renal dysfunction should be reduced as follows: Active Duodenal Ulcer, GERD, and Benign Gastric Ulcer Ccr Dose 20-50 mL/min 150 mg daily <20 mL/min 150 mg every other day Maintenance Therapy Ccr Dose 20-50 mL/min 150 mg every other day <20 mL/min 150 mg every 3 days Some elderly patients may have creatinine clearances of less than 50 mL/min, and, based on pharmacokinetic data in patients with renal impairment, the dose for such patients should be reduced accordingly. The clinical effects of this dosage reduction in patients with renal failure have not been evaluated.
CONTRAINDICATION: Nizatidine is contraindicated in patients with known hypersensitivity to the drug. Because cross sensitivity in this class of compounds has been observed, H 2 -receptor antagonists, including nizatidine, should not be administered to patients with a history of hypersensitivity to other H 2 -receptor antagonists.
Worldwide, controlled clinical trials of nizatidine included over 6,000 patients given nizatidine in studies of varying durations. Placebo-controlled trials in the United States and Canada included over 2,600 patients given nizatidine and over 1,700 given placebo. Among the adverse events in these placebo-controlled trials, anemia (0.2% vs 0%) and urticaria (0.5% vs 0.1%) were significantly more common in the nizatidine group. Incidence in Placebo-Controlled Clinical Trials in the United States and Canada Table 5 lists adverse events that occurred at a frequency of 1% or more among nizatidine-treated patients who participated in placebo-controlled trials. The cited figures provide some basis for estimating the relative contribution of drug and nondrug factors to the side-effect incidence rate in the population studied. Table 5. Incidence of Treatment-Emergent Adverse Events in Placebo-Controlled Clinical Trials in the United States and Canada Percentage of Patients Reporting Event Body System/Adverse Event Events reported by at least 1% of nizatidine-treated patients are included. Nizatidine (N=2,694) Placebo (N=1,729) Body as a Whole Headache 16.6 15.6 Abdominal pain 7.5 12.5 Pain 4.2 3.8 Asthenia 3.1 2.9 Back pain 2.4 2.6 Chest pain 2.3 2.1 Infection 1.7 1.1 Fever 1.6 2.3 Surgical procedure 1.4 1.5 Injury, accident 1.2 0.9 Digestive Diarrhea 7.2 6.9 Nausea 5.4 7.4 Flatulence 4.9 5.4 Vomiting 3.6 5.6 Dyspepsia 3.6 4.4 Constipation 2.5 3.8 Dry mouth 1.4 1.3 Nausea and vomiting 1.2 1.9 Anorexia 1.2 1.6 Gastrointestinal disorder 1.1 1.2 Tooth disorder 1.0 0.8 Musculoskeletal Myalgia 1.7 1.5 Nervous Dizziness 4.6 3.8 Insomnia 2.7 3.4 Abnormal dreams 1.9 1.9 Somnolence 1.9 1.6 Anxiety 1.6 1.4 Nervousness 1.1 0.8 Respiratory Rhinitis 9.8 9.6 Pharyngitis 3.3 3.1 Sinusitis 2.4 2.1 Cough, increased 2.0 2.0 Skin and Appendages Rash 1.9 2.1 Pruritus 1.7 1.3 Special Senses Amblyopia 1.0 0.9 A variety of less common events were also reported; it was not possible to determine whether these were caused by nizatidine. Hepatic Hepatocellular injury, evidenced by elevated liver enzyme tests (SGOT [AST], SGPT [ALT], or alkaline phosphatase), occurred in some patients and was possibly or probably related to nizatidine. In some cases, there was marked elevation of SGOT, SGPT enzymes (greater than 500 IU/L) and, in a single instance, SGPT was greater than 2,000 IU/L. The overall rate of occurrences of elevated liver enzymes and elevations to 3 times the upper limit of normal, however, did not significantly differ from the rate of liver enzyme abnormalities in placebo-treated patients.All abnormalities were reversible after discontinuation of nizatidine. Since market introduction, hepatitis and jaundice have been reported. Rare cases of cholestatic or mixed hepatocellular and cholestatic injury with jaundice have been reported with reversal of the abnormalities after discontinuation of nizatidine. Cardiovascular In clinical pharmacology studies, short episodes of asymptomatic ventricular tachycardia occurred in 2 individuals administered nizatidine and in 3 untreated subjects. CNS Rare cases of reversible mental confusion have been reported. Endocrine Clinical pharmacology studies and controlled clinical trials showed no evidence of antiandrogenic activity due to nizatidine. Impotence and decreased libido were reported with similar frequency by patients who received nizatidine and by those given placebo. Rare reports of gynecomastia occurred. Hematologic Anemia was reported significantly more frequently in nizatidine-than in placebo-treated patients. Fatal thrombocytopenia was reported in a patient who was treated with nizatidine and another H 2 -receptor antagonist. On previous occasions, this patient had experienced thrombocytopenia while taking other drugs. Rare cases of thrombocytopenic purpura have been reported. Integumental Sweating and urticaria were reported significantly more frequently in nizatidine- than in placebo-treated patients. Rash and exfoliative dermatitis were also reported. Vasculitis has been reported rarely. Hypersensitivity As with other H 2 -receptor antagonists, rare cases of anaphylaxis following administration of nizatidine have been reported. Rare episodes of hypersensitivity reactions (eg, bronchospasm, laryngeal edema, rash, and eosinophilia) have been reported. Body as a Whole Serum sickness-like reactions have occurred rarely in conjunction with nizatidine use. Genitourinary Reports of impotence have occurred. Other Hyperuricemia unassociated with gout or nephrolithiasis was reported. Eosinophilia, fever, and nausea related to nizatidine administration have been reported.
No interactions have been observed between nizatidine and theophylline, chlordiazepoxide, lorazepam, lidocaine, phenytoin, and warfarin. Nizatidine does not inhibit the cytochrome P-450-linked drug-metabolizing enzyme system; therefore, drug interactions mediated by inhibition of hepatic metabolism are not expected to occur. In patients given very high doses (3,900 mg) of aspirin daily, increases in serum salicylate levels were seen when nizatidine, 150 mg b.i.d., was administered concurrently.