
İHALE DÜNYASI
İHALE DÜNYASI




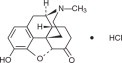
Hydromorphone hydrochloride, a hydrogenated ketone of morphine, is an opioid agonist. Hydromorphone Hydrochloride Injection, USP [high potency formulation (HPF)] is available as a sterile, aqueous solution in AMBER ampules and in AMBER , single-dose vials for intravenous, subcutaneous, or intramuscular administration. Each ampule and single-dose vial contains 10 mg/mL of hydromorphone hydrochloride with 0.2% sodium citrate and 0.2% citric acid added as a buffer to maintain a pH of between 3.5 and 5.5. The chemical name of hydromorphone hydrochloride is 4,5?-epoxy-3-hydroxy-17-methylmorphinan-6-one hydrochloride. The molecular weight is 321.80. Its molecular formula is C 17 H 19 NO 3 *HCl, and it has the following chemical structure: Hydromorphone hydrochloride is a white or almost white crystalline powder that is freely soluble in water, very slightly soluble in ethanol (96%), and practically insoluble in methylene chloride. Chemical Structure
Hydromorphone hydrochloride injection is indicated for the management of pain severe enough to require an opioid analgesic and for which alternate treatments are inadequate. Hydromorphone hydrochloride injection [high potency formulation (HPF)] is indicated for use in opioid-tolerant patients who require higher doses of opioids for the management of pain severe enough to require an opioid analgesic and for which alternate treatments are inadequate. Patients considered opioid tolerant are those who are taking for one week or longer, around-the-clock medicine consisting of at least 60 mg oral morphine per day, or at least 25 mcg transdermal fentanyl per hour, or at least 30 mg oral oxycodone per day, or at least 8 g oral hydromorphone per day, or at least 25 mg oral oxymorphone per day, or at least 60 mg oral hydrocodone per day, or an equianalgesic dose of another opioid for one week or longer. Patients must remain on around-the-clock opioids while administering hydromorphone hydrochloride injection (HPF). Hydromorphone hydrochloride injection is an opioid agonist indicated for the management of pain severe enough to require an opioid analgesic and for which alternate treatments are inadequate. ( 1 ) Hydromorphone hydrochloride injection [high potency formulation (HPF)] is an opioid agonist indicated for use in opioid-tolerant patients who require higher doses of opioids for the management of pain severe enough to require an opioid analgesic and for which alternate treatments are inadequate. Patients considered opioid tolerant are those who are taking, for one week or longer, around-the-clock medicine consisting of at least 60 mg of oral morphine per day, at least 25 mcg/hr of transdermal fentanyl per hour, at least 30 mg of oral oxycodone per day, at least 8 mg of oral hydromorphone per day, at least 25 mg oral oxymorphone per day, at least 60 mg oral hydrocodone per day, or an equianalgesic dose of another opioid daily for a week or longer. Patients must remain on around-the-clock opioids when administering hydromorphone hydrochloride injection (HPF). Limitations of Use: Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, reserve hydromorphone hydrochloride injection [high potency formulation (HPF)] for use in patients for whom alternative treatment options [e.g., non-opioid analgesics or opioid combination products]: Have not been tolerated, or are not expected to be tolerated Have not provided adequate analgesia, or are not expected to provide adequate analgesia Limitations of Use Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses [see Warnings and Precautions ( 5.2 ) ], reserve hydromorphone hydrochloride injection [high potency formulation (HPF)] for use in patients for whom alternative treatment options [e.g., non-opioid analgesics or opioid combination products]: Have not been tolerated, or are not expected to be tolerated Have not provided adequate analgesia, or are not expected to provide adequate analgesia
Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals. Individualize dosing based on the severity of pain, patient response, prior analgesic experience, and risk factors for addiction, abuse, and misuse. ( 2.1 ) Initial Dosage: - Intramuscular or Subcutaneous Use: The usual starting dose is 1 mg to 2 mg every 2 to 3 hours as necessary. ( 2.2 ) - Intravenous Use: The usual starting dose is 0.2 mg to 1 mg every 2 to 3 hours. The injection should be given slowly, over at least 2 to 3 minutes. ( 2.2 ) Hydromorphone hydrochloride injection [high potency formulation (HPF)] is for opioid-tolerant patients only and should be used only if the amount of hydromorphone required can be delivered accurately with this formulation. ( 2.2 ) Hepatic Impairment: Initiate treatment with one-fourth to one-half the usual starting dose, depending on degree of hepatic impairment. ( 2.3 ) Renal Impairment: Initiate treatment with one-fourth to one-half the usual starting dose, depending on degree of renal impairment. ( 2.4 ) Do not stop hydromorphone hydrochloride injection [high potency formulation (HPF)] abruptly in a physically-dependent patient. ( 2.6 ) 2.1 Important Dosage and Administration Instructions Always initiate dosing in opioid-naive patients using hydromorphone hydrochloride injection. Never administer hydromorphone hydrochloride injection [high potency formulation (HPF)] to opioid-naive patients. U se the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions ( 5 ) ]. Initiate the dosing regimen for each patient individually, taking into account the patient's severity of pain, patient response, prior analgesic treatment experience, and risk factors for addiction, abuse, and misuse [see Warnings and Precautions ( 5.2 ) ]. Monitor patients closely for respiratory depression, especially within the first 24 to 72 hours of initiating therapy and following dosage increases with hydromorphone hydrochloride injection (HPF) and adjust the dosage accordingly [see Warnings and Precautions ( 5.3 ) ]. Inspect parenteral drug products visually for particulate matter and discoloration prior to administration, whenever solution and container permit. A slight yellowish discoloration may develop in hydromorphone hydrochloride injection (HPF). No loss of potency has been demonstrated. Hydromorphone hydrochloride injection (HPF) is physically compatible and chemically stable for at least 24 hours at 25°C, protected from light in most common large-volume parenteral solutions. Discard any unused portion in an appropriate manner. 500 mg/50 mL Vial To use this single-dose presentation, withdraw the contents using aseptic technique for preparation of a single, large volume parenteral solution. Discard any unused portion in an appropriate manner. 2.2 Initial Dosage Use of Hydromorphone Hydrochloride Injection [high potency formulation (HPF)] as the First Opioid Analgesic Hydromorphone hydrochloride injection (HPF) is for use in opioid tolerant patients only. Do not use hydromorphone hydrochloride injection (HPF) for patients who are not tolerant to the respiratory depressant or sedating effects of opioids. Subcutaneous or Intramuscular Administration: The usual starting dose of hydromorphone hydrochloride injection is 1 mg to 2 mg every 2 to 3 hours as necessary. Depending on the clinical situation, the initial starting dose may be lowered in patients who are opioid naive. Intravenous Administration: The initial starting dose is 0.2 to 1 mg every 2 to 3 hours. Intravenous administration should be given slowly , over at least 2 to 3 minutes, depending on the dose. The initial dose should be reduced in the elderly or debilitated and may be lowered to 0.2 mg. Conversion From Other Opioids to Hydromorphone Hydrochloride Injection [high potency formulation (HPF)] There is inter-patient variability in the potency of opioid drugs and opioid formulations. Therefore, a conservative approach is advised when determining the total daily dosage of hydromorphone hydrochloride injection (HPF). It is safer to underestimate a patient's 24-hour hydromorphone hydrochloride injection (HPF) dosage than to overestimate the 24-hour hydromorphone hydrochloride injection (HPF) dosage and manage an adverse reaction due to overdose. If the decision is made to convert to hydromorphone hydrochloride injection from another opioid analgesic using publicly available data, convert the current total daily amount(s) of opioid(s) received to an equivalent total daily dose of hydromorphone hydrochloride injection and reduce by one-half due to the possibility of incomplete cross tolerance. Divide the new total amount by the number of doses permitted based on dosing interval (e.g., 8 doses for every-three-hour dosing). Titrate the dose according to the patient's response. Use hydromorphone hydrochloride injection (HPF) ONLY for patients who require the higher concentration and lower total volume of hydromorphone hydrochloride injection (HPF). Because of its high concentration, the delivery of precise doses of hydromorphone hydrochloride injection (HPF) may be difficult if low doses of hydromorphone are required. Therefore, use hydromorphone hydrochloride injection (HPF) only if the amount of hydromorphone required can be delivered accurately with this formulation. Base the starting dose for hydromorphone hydrochloride injection (HPF) on the prior dose of hydromorphone hydrochloride injection or on the prior dose of an alternate opioid. 2.3 Dosage Modifications in Patients with Hepatic Impairment Start patients with hepatic impairment on one-fourth to one-half the usual hydromorphone hydrochloride injection starting dose depending on the extent of impairment [see Clinical Pharmacology ( 12.3 ) ]. 2.4 Dosage Modifications in Patients with Renal Impairment Start patients with renal impairment on one-fourth to one-half the usual hydromorphone hydrochloride injection starting dose depending on the degree of impairment [see Clinical Pharmacology ( 12.3 ) ]. 2.5 Titration and Maintenance of Therapy Individually titrate hydromorphone hydrochloride injection [high potency formulation (HPF)] to a dose that provides adequate analgesia and minimizes adverse reactions. Continually reevaluate patients receiving hydromorphone hydrochloride injection (HPF) to assess the maintenance of pain control and the relative incidence of adverse reactions, as well as monitoring for the development of addiction, abuse, or misuse [see Warnings and Precautions ( 5.2 ) ]. Frequent communication is important among the prescriber, other members of the healthcare team, the patient, and the caregiver/family during periods of changing analgesic requirements, including initial titration. If the level of pain increases after dosage stabilization, attempt to identify the source of increased pain before increasing the hydromorphone hydrochloride injection (HPF) dosage. If unacceptable opioid-related adverse reactions are observed, consider reducing the dosage. Adjust the dosage to obtain an appropriate balance between management of pain and opioid-related adverse reactions. 2.6 Discontinuation of Hydromorphone Hydrochloride Injection (HPF) When a patient who has been taking hydromorphone hydrochloride injection [high potency formulation (HPF)] regularly and may be physically dependent no longer requires therapy with hydromorphone hydrochloride injection (HPF), taper the dose gradually, by 25% to 50% every 2 to 4 days, while monitoring carefully for signs and symptoms of withdrawal. If the patient develops these signs or symptoms, raise the dose to the previous level and taper more slowly, either by increasing the interval between decreases, decreasing the amount of change in dose, or both. Do not abruptly discontinue hydromorphone hydrochloride injection (HPF) in a physically-dependent patient [see Warnings and Precautions ( 5.12 ), Drug Abuse and Dependence ( 9.3 ) ].
Hydromorphone hydrochloride injection [high potency formulation (HPF)] is contraindicated in patients with: Significant respiratory depression [see Warnings and Precautions ( 5.3 ) ] Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions ( 5.3 ) ] Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions ( 5.10 ) ] Hypersensitivity to hydromorphone, hydromorphone salts, any other components of the product, or sulfite containing medications (e.g., anaphylaxis) [see Warnings and Precautions ( 5.14 ) ] Hydromorphone hydrochloride injection (HPF) is contraindicated in patients who are not opioid tolerant [see Warnings and Precautions ( 5.1 ) ]. Significant respiratory depression. ( 4 ) Acute or severe bronchial asthma in an unmonitored setting or in absence of resuscitative equipment. ( 4 ) Known or suspected gastrointestinal obstruction, including paralytic ileus. ( 4 ) Known hypersensitivity to hydromorphone, hydromorphone salts, sulfite-containing medications, or any other components of the product. ( 4 ) Hydromorphone hydrochloride injection [high potency formulation (HPF)]: Patients who are not opioid tolerant. ( 4 )
The following serious adverse reactions are described, or described in greater detail, in other sections: Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.2 ) ] Life-Threatening Respiratory Depression [see Warnings and Precautions ( 5.3 ) ] Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.4 ) ] Interactions with Benzodiazepines and Other CNS Depressants [see Warnings and Precautions ( 5.5 ) ] Adrenal Insufficiency [see Warnings and Precautions ( 5.7 ) ] Severe Hypotension [see Warnings and Precautions ( 5.8 ) ] Seizures [see Warnings and Precautions ( 5.11 ) ] Gastrointestinal Adverse Reactions [see Warnings and Precautions ( 5.10 ) ] Withdrawal [see Warnings and Precautions ( 5.12 ) ] The following adverse reactions associated with the use of hydromorphone were identified in clinical studies or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Serious adverse reactions associated with hydromorphone hydrochloride injection [high potency formulation (HPF)] include respiratory depression and apnea and, to a lesser degree, circulatory depression, respiratory arrest, shock, and cardiac arrest. The most common adverse effects are lightheadedness, dizziness, sedation, nausea, vomiting, sweating, flushing, dysphoria, euphoria, dry mouth, and pruritus. These effects seem to be more prominent in ambulatory patients and in those not experiencing severe pain. Most common adverse reactions are lightheadedness, dizziness, sedation, nausea, vomiting, sweating, flushing, dysphoria, euphoria, dry mouth, and pruritus. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Akorn, Inc. at 1-800-932-5676 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . Less Frequently Observed Adverse Reactions Cardiac disorders: tachycardia, bradycardia, palpitations Eye disorders: vision blurred, diplopia, miosis, visual impairment Gastrointestinal disorders: constipation, ileus, diarrhea, abdominal pain General disorders and administration site conditions: weakness, feeling abnormal, chills, injection site urticaria, fatigue, injection site reactions, peripheral edema Hepatobiliary disorders: biliary colic Immune system disorders: anaphylactic reactions, hypersensitivity reactions Investigations: hepatic enzymes increased Metabolism and nutrition disorders: decreased appetite Musculoskeletal and connective tissue disorders: muscle rigidity Nervous system disorders: headache, tremor, paresthesia, nystagmus, increased intracranial pressure, syncope, taste alteration, involuntary muscle contractions, presyncope, convulsion, drowsiness, dyskinesia, hyperalgesia, lethargy, myoclonus, somnolence Psychiatric disorders: agitation, mood altered, nervousness, anxiety, depression, hallucination, disorientation, insomnia, abnormal dreams Renal and urinary disorders: urinary retention, urinary hesitation, antidiuretic effects Reproductive system and breast disorders: erectile dysfunction Respiratory, thoracic, and mediastinal disorders: bronchospasm, laryngospasm, dyspnea, oropharyngeal swelling Skin and subcutaneous tissue disorders: injection site pain, urticaria, rash, hyperhidrosis Vascular disorders: flushing, hypotension, hypertension Serotonin syndrome: Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs. Adrenal insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Anaphylaxis: Anaphylaxis has been reported with ingredients contained in hydromorphone hydrochloride injection [high potency formulation (HPF)]. Androgen deficiency: Cases of androgen deficiency have occurred with chronic use of opioids [see Clinical Pharmacology ( 12.2 ) ].
Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients: Monitor closely, particularly during initiation and titration. ( 5.6 ) Adrenal Insufficiency: If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.7 ) Severe Hypotension: Monitor during dosage initiation and titration. Avoid use of hydromorphone hydrochloride injection [high potency formulation (HPF)] in patients with circulatory shock. ( 5.8 ) Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness: Monitor for sedation and respiratory depression. Avoid use of hydromorphone hydrochloride injection (HPF) in patients with impaired consciousness or coma. ( 5.9 ) Hydromorphone hydrochloride injection (HPF) contains sodium metabisulfite. There is a risk of anaphylactic symptoms and life-threatening asthmatic episodes in susceptible people. ( 5.14 ) 5.1 Risk of Medication Errors Hydromorphone hydrochloride injection [high potency formulation (HPF)] is a 10 mg/mL concentrated solution of hydromorphone, and is intended for use in opioid-tolerant patients only. Patients considered opioid tolerant are those who are taking at least 60 mg oral morphine/day, 25 mcg transdermal fentanyl/hour, 30 mg oral oxycodone/ day, 8 mg oral hydromorphone/day, 25 mg oral oxymorphone/day, or an equianalgesic dose of another opioid for one week or longer. Do not confuse hydromorphone hydrochloride injection (HPF) with standard parenteral formulations of hydromorphone hydrochloride injection (1 mg/mL, 2 mg/mL, 4 mg/mL) or other opioids, as overdose and death could result. 5.2 Addiction, Abuse, and Misuse Hydromorphone hydrochloride injection [high potency formulation (HPF)] contains hydromorphone, a Schedule II controlled substance. As an opioid, hydromorphone hydrochloride injection (HPF) exposes users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence ( 9 ) ]. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed hydromorphone hydrochloride injection (HPF). Addiction can occur at recommended dosages and if the drug is misused or abused. Assess each patient's risk for opioid addiction, abuse, or misuse prior to prescribing hydromorphone hydrochloride injection (HPF), and monitor all patients receiving hydromorphone hydrochloride injection (HPF) for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as hydromorphone hydrochloride injection (HPF), but use in such patients necessitates intensive counseling about the risks and proper use of hydromorphone hydrochloride injection (HPF) along with intensive monitoring for signs of addiction, abuse, and misuse. Opioids are sought by drug abusers and people with addiction disorders and are subject to criminal diversion. Consider these risks when prescribing or dispensing hydromorphone hydrochloride injection (HPF). Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity. Contact local state professional licensing board or state controlled substances authority for information on how to prevent and detect abuse or diversion of this product. 5.3 Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient's clinical status [see Overdosage ( 10 ) ]. Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of hydromorphone hydrochloride injection [high potency formulation (HPF)], the risk is greatest during the initiation of therapy or following a dosage increase. Monitor patients closely for respiratory depression, especially within the first 24 to 72 hours of initiating therapy with and following dosage increases of hydromorphone hydrochloride injection (HPF). To reduce the risk of respiratory depression, proper dosing and titration of hydromorphone hydrochloride injection (HPF) are essential [see Dosage and Administration ( 2 ) ]. Overestimating the hydromorphone hydrochloride injection (HPF) dosage when converting patients from another opioid product can result in a fatal overdose with the first dose. Hydromorphone hydrochloride injection (HPF) is for use in opioid-tolerant patients only . Administration of this formulation may cause fatal respiratory depression when administered to patients who are not tolerant to the respiratory depressant effects of opioids. Opioids can cause sleep-related breathing disorders including central sleep apnea (CSA) and sleep-related hypoxemia. Opioid use increases the risk of CSA in a dose-dependent fashion. In patients who present with CSA, consider decreasing the opioid dosage using best practices for opioid taper [see Dosage and Administration ( 2.6 ) ]. 5.4 Neonatal Opioid Withdrawal Syndrome Prolonged use of hydromorphone hydrochloride injection [high potency formulation (HPF)] during pregnancy can result in withdrawal in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening if not recognized and treated, and requires management according to protocols developed by neonatology experts. Observe newborns for signs of neonatal opioid withdrawal syndrome and manage accordingly. Advise pregnant women using opioids for a prolonged period of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available [see Use in Specific Populations ( 8.1 ), Patient Counseling Information ( 17 ) ]. 5.5 Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Profound sedation, respiratory depression, coma, and death may result from the concomitant use of hydromorphone hydrochloride injection [high potency formulation (HPF)] with benzodiazepines or other CNS depressants (e.g., nonbenzodiazepine sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, other opioids, alcohol). Because of these risks, reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics [see Drug Interactions ( 7 ) ]. If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation. Advise both patients and caregivers about the risks of respiratory depression and sedation when hydromorphone hydrochloride injection (HPF) is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs [see Drug Interactions ( 7 ) and Patient Counseling Information ( 17 ) ]. 5.6 Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients The use of hydromorphone hydrochloride injection [high potency formulation (HPF)] in patients with acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment is contraindicated. Patients with Chronic Pulmonary Disease Hydromorphone hydrochloride injection [high potency formulation (HPF)] treated patients with significant chronic obstructive pulmonary disease or cor pulmonale, and those with a substantially decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression are at increased risk of decreased respiratory drive including apnea, even at recommended dosages of hydromorphone hydrochloride injection (HPF) [see Warnings and Precautions ( 5.3 ) ]. Elderly, Cachectic, or Debilitated Patients Life-threatening respiratory depression is more likely to occur in elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients [see Warnings and Precautions ( 5.3 ) ]. Monitor such patients closely, particularly when initiating and titrating hydromorphone hydrochloride injection [high potency formulation (HPF)] and when hydromorphone hydrochloride injection (HPF) is given concomitantly with other drugs that depress respiration [see Warnings and Precautions ( 5.3 ) ]. Alternatively, consider the use of nonopioid analgesics in these patients. 5.7 Adrenal Insufficiency Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency. 5.8 Severe Hypotension Hydromorphone hydrochloride injection [high potency formulation (HPF)] may cause severe hypotension including orthostatic hypotension and syncope in ambulatory patients. There is increased risk in patients whose ability to maintain blood pressure has already been compromised by a reduced blood volume or concurrent administration of certain CNS depressant drugs (e.g., phenothiazines or general anesthetics) [see Drug Interactions ( 7 ) ]. Monitor these patients for signs of hypotension after initiating or titrating the dosage of hydromorphone hydrochloride injection (HPF). In patients with circulatory shock, hydromorphone hydrochloride injection (HPF) may cause vasodilation that can further reduce cardiac output and blood pressure. Avoid the use of hydromorphone hydrochloride injection (HPF) in patients with circulatory shock. 5.9 Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness In patients who may be susceptible to the intracranial effects of CO 2 retention (e.g., those with evidence of increased intracranial pressure or brain tumors), hydromorphone hydrochloride injection [high potency formulation (HPF)] may reduce respiratory drive, and the resultant CO 2 retention can further increase intracranial pressure. Monitor such patients for signs of sedation and respiratory depression, particularly when initiating therapy hydromorphone hydrochloride injection (HPF). Opioids may also obscure the clinical course in a patient with a head injury. Avoid the use of hydromorphone hydrochloride injection (HPF) in patients with impaired consciousness or coma. 5.10 Risks of Use in Patients with Gastrointestinal Conditions Hydromorphone hydrochloride injection [high potency formulation (HPF)] is contraindicated in patients with known or suspected gastrointestinal obstruction, including paralytic ileus. The hydromorphone in hydromorphone hydrochloride injection (HPF) may cause spasm of the sphincter of Oddi. Opioids may cause increases in serum amylase. Monitor patients with biliary tract disease, including acute pancreatitis, for worsening symptoms. 5.11 Increased Risk of Seizures in Patients with Seizure Disorders The hydromorphone in hydromorphone hydrochloride injection [high potency formulation (HPF)] may increase the frequency of seizures in patients with seizure disorders, and may increase the risk of seizures occurring in other clinical settings associated with seizures. Monitor patients with a history of seizure disorders for worsened seizure control during hydromorphone hydrochloride injection (HPF) therapy. 5.12 Withdrawal Avoid the use of mixed agonist/antagonist (e.g., pentazocine, nalbuphine, and butorphanol) or partial agonist (e.g., buprenorphine) analgesics in patients who are receiving a full opioid agonist analgesic, including hydromorphone hydrochloride injection [high potency formulation (HPF)]. In these patients, mixed agonist/antagonist and partial agonist analgesics may reduce the analgesic effect and/or precipitate withdrawal symptoms [see Drug Interactions ( 7 ) ]. When discontinuing hydromorphone hydrochloride injection [high potency formulation (HPF)], in a physicallydependent patient, gradually taper the dosage [see Dosage and Administration ( 2.6 ) ]. Do not abruptly discontinue hydromorphone hydrochloride injection (HPF) in these patients [see Drug Abuse and Dependence ( 9.3 ) ]. 5.13 Risks of Driving and Operating Machinery Hydromorphone hydrochloride injection (HPF) may impair the mental or physical abilities needed to perform potentially hazardous activities such as driving a car or operating machinery. Warn patients not to drive or operate dangerous machinery unless they are tolerant to the effects of hydromorphone hydrochloride injection (HPF) and know how they will react to the medication [see Patient Counseling Information ( 17 ) ]. 5.14 Sulfites Hydromorphone hydrochloride injection (HPF) contain sodium metabisulfite, a sulfite that may cause allergictype reactions including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in certain susceptible people. The overall prevalence of sulfite sensitivity in the general population is unknown and probably low. Sulfite sensitivity is seen more frequently in asthmatic than in nonasthmatic people. 5.15 Increased Risk of Hypotension and Respiratory Depression with Rapid Intravenous Administration Hydromorphone hydrochloride injection [high potency formulation (HPF)] may be given intravenously, but the injection should be given very slowly. Rapid intravenous injection of opioid analgesics increases the possibility of side effects such as hypotension and respiratory depression [see Dosage and Administration ( 2 ) ]. --- BOXED WARNING: WARNING: RISK OF MEDICATION ERRORS; ADDICTION, ABUSE, AND MISUSE; LIFE-THREATENING RESPIRATORY DEPRESSION; NEONATAL OPIOID WITHDRAWAL SYNDROME; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS WARNING: RISK OF MEDICATION ERRORS; ADDICTION, ABUSE, AND MISUSE; LIFE-THREATENING RESPIRATORY DEPRESSION; NEONATAL OPIOID WITHDRAWAL SYNDROME; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS See full prescribing information for complete boxed warning. Do not confuse hydromorphone hydrochloride injection [high potency formulation (HPF)] with standard parenteral formulations of hydromorphone hydrochloride injection or other opioids, as overdose and death could result. ( 5.1 ) Hydromorphone hydrochloride injection [high potency formulation (HPF)] exposes users to risks of addictions, abuse, and misuse, which can lead to overdose and death. Assess patient's risk before prescribing and monitor regularly for these behaviors and conditions. ( 5.2 ) Serious, life-threatening, or fatal respiratory depression may occur. Monitor closely, especially upon initiation or following a dose increase. ( 5.3 ) Prolonged use of hydromorphone hydrochloride injection [high potency formulation (HPF)] during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated. If prolonged opioid use is required in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available. ( 5.4 ) Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate; limit dosages and durations to the minimum required; and follow patients for signs and symptoms of respiratory depression and sedation. ( 5.5 , 7 ) Risk of Medication Errors Hydromorphone hydrochloride injection [high potency formulation (HPF)] is a more concentrated solution of hydromorphone than hydromorphone hydrochloride injection, and is for use in opioid-tolerant patients only. Do not confuse hydromorphone hydrochloride injection [high potency formulation (HPF)] with standard parenteral formulations of hydromorphone hydrochloride injection or other opioids, as overdose and death could result [see Warnings and Precautions ( 5.1 ) ]. Addiction, Abuse, and Misuse Hydromorphone hydrochloride injection [high potency formulation (HPF)] exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Assess each patient's risk prior to prescribing hydromorphone hydrochloride injection [high potency formulation (HPF)] and monitor all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions ( 5.2 ) ]. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of hydromorphone hydrochloride injection [high potency formulation (HPF)]. Monitor for respiratory depression, especially during initiation of hydromorphone hydrochloride injection [high potency formulation (HPF)] or following a dose increase [see Warnings and Precautions ( 5.3 ) ]. Neonatal Opioid Withdrawal Syndrome Prolonged use of hydromorphone hydrochloride injection [high potency formulation (HPF)] during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated, and requires management according to protocols developed by neonatology experts. If opioid use is required for a prolonged period in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available [see Warnings and Precautions ( 5.4 ) ]. Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death [see Warnings and Precautions ( 5.5 ), Drug Interactions ( 7 ) ]. Reserve concomitant prescribing of hydromorphone hydrochloride [high potency formulation (HPF)] and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients for signs and symptoms of respiratory depression and sedation.
Table 1 includes clinically significant drug interactions with hydromorphone hydrochloride injection [high potency formulation (HPF)]. TABLE 1. Clinically Significant Drug Interactions with Hydromorphone Hydrochloride Injection [high potency formulation (HPF)] Benzodiazepines and other Central Nervous System Depressants (CNS) Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines and other CNS depressants, including alcohol, can increase the risk of hypotension, respiratory depression, profound sedation, coma, and death. Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation [see Warnings and Precautions ( 5.3 ) ]. Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, other opioids, alcohol. Serotonergic Drugs Clinical Impact: The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system has resulted in serotonin syndrome. Intervention: If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment. Discontinue hydromorphone hydrochloride injection (HPF) if serotonin syndrome is suspected. Examples: Selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), triptans, 5-HT3 receptor antagonists, drugs that effect the serotonin neurotransmitter system (e.g., mirtazapine, trazodone, tramadol), certain muscle relaxants (i.e., cyclobenzaprine, metaxalone), monoamine oxidase (MAO) inhibitors (those intended to treat psychiatric disorders and also others, such as linezolid and intravenous methylene blue). Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: MAOI interactions with opioids may manifest as serotonin syndrome or opioid toxicity (e.g., respiratory depression, coma) [see Warnings and Precautions ( 5.3 ) ]. If urgent use of an opioid is necessary, use test doses and frequent titration of small doses to treat pain while closely monitoring blood pressure and signs and symptoms of CNS and respiratory depression. Intervention: The use of hydromorphone hydrochloride injection (HPF) is not recommended for patients taking MAOIs or within 14 days of stopping such treatment. Examples: phenelzine, tranylcypromine, linezolid Mixed Agonist/Antagonist and Partial Agonist Opioid Analgesics Clinical Impact: May reduce the analgesic effect of hydromorphone hydrochloride injection (HPF) and/or precipitate withdrawal syndrome. Intervention: Avoid concomitant use. Examples: butorphanol, nalbuphine, pentazocine, buprenorphine Muscle Relaxants Clinical Impact: Hydromorphone may enhance the neuromuscular blocking action of skeletal muscle relaxants and produce an increased degree of respiratory depression. Intervention: Monitor patients for signs of respiratory depression that may be greater than otherwise expected and decrease the dosage of hydromorphone hydrochloride injection (HPF) and/ or the muscle relaxant as necessary. Diuretics Clinical Impact: Opioids can reduce the efficacy of diuretics by inducing the release of antidiuretic hormone. Intervention: Monitor patients for signs of diminished diuresis and/or effects on blood pressure and increase the dosage of the diuretic as needed. Anticholinergic Drugs Clinical Impact: The concomitant use of anticholinergic drugs may increase risk of urinary retention and/or severe constipation, which may lead to paralytic ileus. Intervention: Monitor patients for signs of urinary retention or reduced gastric motility when hydromorphone hydrochloride injection (HPF) is used concomitantly with anticholinergic drugs. Serotonergic Drugs: Concomitant use may result in serotonin syndrome. Discontinue hydromorphone hydrochloride injection [high potency formulation (HPF)] if serotonin syndrome is suspected. ( 7 ) Monoamine Oxidase Inhibitors (MAOIs): Can potentiate the effects of hydromorphone. Avoid concomitant use in patients receiving MAOIs or within 14 days of stopping treatment with an MAOI. ( 7 ) Mixed Agonist/Antagonist and Partial Agonist Opioid Analgesics: Avoid use with hydromorphone hydrochloride injection (HPF) because it may reduce analgesic effect of hydromorphone hydrochloride injection (HPF) or precipitate withdrawal symptoms. ( 7 )