
İHALE DÜNYASI
İHALE DÜNYASI

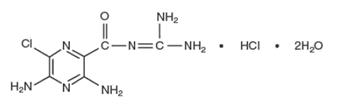
Amiloride hydrochloride, an antikaliuretic-diuretic agent, is a pyrazine-carbonyl-guanidine that is unrelated chemically to other known antikaliuretic or diuretic agents. It is the salt of a moderately strong base (pKa 8.7). It is designated chemically as 3,5-diamino-6-chloro-N-(diaminomethylene) pyrazinecarboxamide monohydrochloride, dihydrate and has a molecular weight of 302.12. Its molecular formula is C 6 H 8 CIN 7 O*HCl*2H 2 O and its structural formula is: Amiloride hydrochloride is a pale-yellow to greenish-yellow powder. It is freely soluble in dimethylsulphoxide; slightly soluble in water, ethyl alcohol and isopropyl alcohol; sparingly soluble in methyl alcohol; practically insoluble in acetone, chloroform, diethyl ether and ethyl acetate. Each amiloride hydrochloride tablet intended for oral administration contains 5 mg of amiloride hydrochloride, calculated on the anhydrous basis. In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, D&C yellow #10 aluminum lake, dibasic calcium phosphate dihydrate, FD & C yellow #6 aluminum lake, magnesium stearate, microcrystalline cellulose and povidone. structure
Amiloride hydrochloride tablets are indicated as adjunctive treatment with thiazide diuretics or other kaliuretic-diuretic agents in congestive heart failure or hypertension to: a. help restore normal serum potassium levels in patients who develop hypokalemia on the kaliuretic diuretic. b. prevent development of hypokalemia in patients who would be exposed to particular risk if hypokalemia were to develop, e.g., digitalized patients or patients with significant cardiac arrhythmias. The use of potassium-conserving agents is often unnecessary in patients receiving diuretics for uncomplicated essential hypertension when such patients have a normal diet. Amiloride hydrochloride has little additive diuretic or antihypertensive effect when added to a thiazide diuretic. Amiloride hydrochloride tablets should rarely be used alone. It has weak (compared with thiazides) diuretic and antihypertensive effects. Used as single agents, potassium sparing diuretics, including amiloride hydrochloride, result in an increased risk of hyperkalemia (approximately 10% with amiloride). Amiloride hydrochloride tablets should be used alone only when persistent hypokalemia has been documented and only with careful titration of the dose and close monitoring of serum electrolytes.
Amiloride hydrochloride should be administered with food. Amiloride hydrochloride, one 5 mg tablet daily, should be added to the usual antihypertensive or diuretic dosage of a kaliuretic diuretic. The dosage may be increased to 10 mg per day, if necessary. More than two 5 mg tablets of amiloride hydrochloride daily usually are not needed, and there is little controlled experience with such doses. If persistent hypokalemia is documented with 10 mg, the dose can be increased to 15 mg, then 20 mg, with careful monitoring of electrolytes. In treating patients with congestive heart failure after an initial diuresis has been achieved, potassium loss may also decrease and the need for amiloride hydrochloride should be re-evaluated. Dosage adjustment may be necessary. Maintenance therapy may be on an intermittent basis. If it is necessary to use amiloride hydrochloride alone (see INDICATIONS ), the starting dosage should be one 5 mg tablet daily. This dosage may be increased to 10 mg per day, if necessary. More than two 5 mg tablets usually are not needed, and there is little controlled experience with such doses. If persistent hypokalemia is documented with 10 mg, the dose can be increased to 15 mg, then 20 mg, with careful monitoring of electrolytes.
Hyperkalemia Amiloride hydrochloride tablets should not be used in the presence of elevated serum potassium levels (greater than 5.5 mEq per liter). Antikaliuretic Therapy or Potassium Supplementation Amiloride hydrochloride should not be given to patients receiving other potassium-conserving agents, such as spironolactone or triamterene. Potassium supplementation in the form of medication, potassium-containing salt substitutes or a potassium-rich diet should not be used with amiloride hydrochloride except in severe and/or refractory cases of hypokalemia. Such concomitant therapy can be associated with rapid increases in serum potassium levels. If potassium supplementation is used, careful monitoring of the serum potassium level is necessary. Impaired Renal Function Anuria, acute or chronic renal insufficiency, and evidence of diabetic nephropathy are contraindications to the use of amiloride hydrochloride. Patients with evidence of renal functional impairment (blood urea nitrogen [BUN] levels over 30 mg per 100 mL or serum creatinine levels over 1.5 mg per 100 mL) or diabetes mellitus should not receive the drug without careful, frequent and continuing monitoring of serum electrolytes, creatinine, and BUN levels. Potassium retention associated with the use of an antikaliuretic agent is accentuated in the presence of renal impairment and may result in the rapid development of hyperkalemia. Hypersensitivity Amiloride hydrochloride is contraindicated in patients who are hypersensitive to this product. | Hyperkalemia Amiloride hydrochloride tablets should not be used in the presence of elevated serum potassium levels (greater than 5.5 mEq per liter). | Antikaliuretic Therapy or Potassium Supplementation Amiloride hydrochloride should not be given to patients receiving other potassium-conserving agents, such as spironolactone or triamterene. Potassium supplementation in the form of medication, potassium-containing salt substitutes or a potassium-rich diet should not be used with amiloride hydrochloride except in severe and/or refractory cases of hypokalemia. Such concomitant therapy can be associated with rapid increases in serum potassium levels. If potassium supplementation is used, careful monitoring of the serum potassium level is necessary. | Impaired Renal Function Anuria, acute or chronic renal insufficiency, and evidence of diabetic nephropathy are contraindications to the use of amiloride hydrochloride. Patients with evidence of renal functional impairment (blood urea nitrogen [BUN] levels over 30 mg per 100 mL or serum creatinine levels over 1.5 mg per 100 mL) or diabetes mellitus should not receive the drug without careful, frequent and continuing monitoring of serum electrolytes, creatinine, and BUN levels. Potassium retention associated with the use of an antikaliuretic agent is accentuated in the presence of renal impairment and may result in the rapid development of hyperkalemia. | Hypersensitivity Amiloride hydrochloride is contraindicated in patients who are hypersensitive to this product.
Amiloride hydrochloride is usually well tolerated and, except for hyperkalemia (serum potassium levels greater than 5.5 mEq per liter - see WARNINGS ), significant adverse effects have been reported infrequently. Minor adverse reactions were reported relatively frequently (about 20%) but the relationship of many of the reports to amiloride hydrochloride is uncertain and the overall frequency was similar in hydrochlorothiazide treated groups. Nausea/anorexia, abdominal pain, flatulence, and mild skin rash have been reported and probably are related to amiloride. Other adverse experiences that have been reported with amiloride are generally those known to be associated with diuresis, or with the underlying disease being treated. The adverse reactions for amiloride hydrochloride listed in the following table have been arranged into two groups: (1) incidence greater than one percent; and (2) incidence one percent or less. The incidence for group (1) was determined from clinical studies conducted in the United States (837 patients treated with amiloride hydrochloride). The adverse effects listed in group (2) include reports from the same clinical studies and voluntary reports since marketing. The probability of a causal relationship exists between amiloride hydrochloride and these adverse reactions, some of which have been reported only rarely. Incidence > 1% Incidence ? 1% Body as a Whole Headache* Back pain Weakness Chest pain Fatigability Neck/shoulder ache Pain, extremities Cardiovascular None Angina pectoris Orthostatic hypotension Arrhythmia Palpitation Digestive Nausea/anorexia* Jaundice Diarrhea* GI bleeding Vomiting* Abdominal fullness Abdominal pain GI disturbance Gas pain Thirst Appetite changes Heartburn Constipation Flatulence Dyspepsia Metabolic Elevated serum potassium levels (>5.5 mEq per liter)** None Skin None Skin rash Itching Dryness of mouth Pruritus Alopecia Musculoskeletal Muscle cramps Joint pain Leg ache Nervous Dizziness Paresthesia Encephalopathy Tremors Vertigo Psychiatric None Nervousness Mental confusion Insomnia Decreased libido Depression Somnolence Respiratory Cough Shortness of Breath Dyspnea Special Senses None Visual disturbances Nasal congestion Tinnitus Increased intraocular pressure Urogenital Impotence Polyuria Dysuria Urinary frequency Bladder spasms Gynecomastia *Reactions occurring in 3% to 8% of patients treated with amiloride hydrochloride. (Those reactions occurring in less than 3% of the patients are unmarked.) **See WARNINGS . Causal Relationship Unknown Other reactions have been reported but occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, that possibility cannot be excluded. Therefore, these observations are listed to serve as alerting information to physicians. Activation of probable pre-existing peptic ulcer Aplastic anemia Neutropenia Abnormal liver function
BOXED WARNING: Hyperkalemia Like other potassium-conserving agents, amiloride may cause hyperkalemia (serum potassium levels greater than 5.5 mEq per liter) which, if uncorrected, is potentially fatal. Hyperkalemia occurs commonly (about 10%) when amiloride is used without a kaliuretic diuretic. This incidence is greater in patients with renal impairment, diabetes mellitus (with or without recognized renal insufficiency), and in the elderly. When amiloride hydrochloride is used concomitantly with a thiazide diuretic in patients without these complications, the risk of hyperkalemia is reduced to about 1 to 2 percent. It is thus essential to monitor serum potassium levels carefully in any patient receiving amiloride, particularly when it is first introduced, at the time of diuretic dosage adjustments, and during any illness that could affect renal function. | Hyperkalemia Like other potassium-conserving agents, amiloride may cause hyperkalemia (serum potassium levels greater than 5.5 mEq per liter) which, if uncorrected, is potentially fatal. Hyperkalemia occurs commonly (about 10%) when amiloride is used without a kaliuretic diuretic. This incidence is greater in patients with renal impairment, diabetes mellitus (with or without recognized renal insufficiency), and in the elderly. When amiloride hydrochloride is used concomitantly with a thiazide diuretic in patients without these complications, the risk of hyperkalemia is reduced to about 1 to 2 percent. It is thus essential to monitor serum potassium levels carefully in any patient receiving amiloride, particularly when it is first introduced, at the time of diuretic dosage adjustments, and during any illness that could affect renal function.
When amiloride hydrochloride is administered concomitantly with an angiotensin-converting enzyme inhibitor, an angiotensin II receptor antagonist, cyclosporine or tacrolimus, the risk of hyperkalemia may be increased. Therefore, if concomitant use of these agents is indicated because of demonstrated hypokalemia, they should be used with caution and with frequent monitoring of serum potassium. (See WARNINGS ). Lithium generally should not be given with diuretics because they reduce its renal clearance and add a high risk of lithium toxicity. Read circulars for lithium preparations before use of such concomitant therapy. In some patients, the administration of a non-steroidal anti-inflammatory agent can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. Therefore, when amiloride hydrochloride and non-steroidal anti-inflammatory agents are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained. Since indomethacin and potassium-sparing diuretics, including amiloride hydrochloride, may each be associated with increased serum potassium levels, the potential effects on potassium kinetics and renal function should be considered when these agents are administered concurrently.