
İHALE DÜNYASI
İHALE DÜNYASI

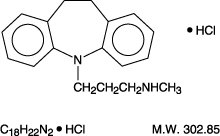
Desipramine hydrochloride USP is an antidepressant drug of the tricyclic type available as tablets of 10 mg, 25 mg, 50 mg, 75 mg, 100 mg or 150 mg for oral administration. Its chemical name is 5 H -Dibenz[ bf ]azepine-5-propanamine, 10, 11-dihydro- N -methyl-, monohydrochloride. Inactive ingredients: hydroxypropyl cellulose, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, starch (corn), and titanium dioxide. Desipramine HCl chemical structure
Desipramine hydrochloride is indicated for the treatment of depression.
Not recommended for use in children (see WARNINGS ). Lower dosages are recommended for elderly patients and adolescents. Lower dosages are also recommended for outpatients compared to hospitalized patients, who are closely supervised. Dosage should be initiated at a low level and increased according to clinical response and any evidence of intolerance. Following remission, maintenance medication may be required for a period of time and should be at the lowest dose that will maintain remission. Usual Adult Dose The usual adult dose is 100 to 200 mg per day. In more severely ill patients, dosage may be further increased gradually to 300 mg/day if necessary. Dosages above 300 mg/day are not recommended. Dosage should be initiated at a lower level and increased according to tolerance and clinical response. Treatment of patients requiring as much as 300 mg should generally be initiated in hospitals, where regular visits by the physician, skilled nursing care, and frequent electrocardiograms (ECG's) are available. The best available evidence of impending toxicity from very high doses of desipramine is prolongation of the QRS or QT intervals on the ECG. Prolongation of the PR interval is also significant, but less closely correlated with plasma levels. Clinical symptoms of intolerance, especially drowsiness, dizziness, and postural hypotension, should also alert the physician to the need for reduction in dosage. Initial therapy may be administered in divided doses or a single daily dose. Maintenance therapy may be given on a once-daily schedule for patient convenience and compliance. Adolescent and Geriatric Dose The usual adolescent and geriatric dose is 25 to 100 mg daily. Dosage should be initiated at a lower level and increased according to tolerance and clinical response to a usual maximum of 100 mg daily. In more severely ill patients, dosage may be further increased to 150 mg/day. Doses above 150 mg/day are not recommended in these age groups. Initial therapy may be administered in divided doses or a single daily dose. Maintenance therapy may be given on a once-daily schedule for patient convenience and compliance.
Desipramine hydrochloride should not be given in conjunction with, or within 2 weeks of, treatment with an MAO inhibitor drug; hyperpyretic crises, severe convulsions, and death have occurred in patients taking MAO inhibitors and tricyclic antidepressants. When desipramine hydrochloride is substituted for an MAO inhibitor, at least 2 weeks should elapse between treatments. Desipramine hydrochloride should then be started cautiously and should be increased gradually. Desipramine hydrochloride is contraindicated in the acute recovery period following myocardial infarction. It should not be used in those who have shown prior hypersensitivity to the drug. Cross-sensitivity between this and other dibenzazepines is a possibility.
Included in the following listing are a few adverse reactions that have not been reported with this specific drug. However, the pharmacologic similarities among the tricyclic antidepressant drugs require that each of the reactions be considered when desipramine hydrochloride is given. Cardiovascular Hypotension, hypertension, palpitations, heart block, myocardial infarction, stroke, arrhythmias, premature ventricular contractions, tachycardia, ventricular tachycardia, ventricular fibrillation, sudden death. There has been a report of an "acute collapse" and "sudden death" in an 8-year old (18 kg) male, treated for 2 years for hyperactivity. There have been additional reports of sudden death in children (see PRECAUTIONS : Pediatric Use ). Psychiatric Confusional states (especially in the elderly) with hallucinations, disorientation, delusions; anxiety, restlessness, agitation; insomnia and nightmares; hypomania; exacerbation of psychosis. Neurologic Numbness, tingling, paresthesias of extremities; incoordination, ataxia, tremors; peripheral neuropathy; extrapyramidal symptoms; seizures; alterations in EEG patterns; tinnitus. Symptoms attributed to Neuroleptic Malignant Syndrome have been reported during desipramine use with and without concomitant neuroleptic therapy. Anticholinergic Dry mouth, and rarely associated sublingual adenitis; blurred vision, disturbance of accommodation, mydriasis, increased intraocular pressure; constipation, paralytic ileus; urinary retention, delayed micturition, dilation of urinary tract. Allergic Skin rash, petechiae, urticaria, itching, photosensitization (avoid excessive exposure to sunlight), edema (of face and tongue or general), drug fever, cross-sensitivity with other tricyclic drugs. Hematologic Bone marrow depressions including agranulocytosis, eosinophilia, purpura, thrombocytopenia. Gastrointestinal Anorexia, nausea and vomiting, epigastric distress, peculiar taste, abdominal cramps, diarrhea, stomatitis, black tongue, hepatitis, jaundice (simulating obstructive), altered liver function, elevated liver function tests, increased pancreatic enzymes. Endocrine Gynecomastia in the male, breast enlargement and galactorrhea in the female; increased or decreased libido, impotence, painful ejaculation, testicular swelling; elevation or depression of blood sugar levels; syndrome of inappropriate antidiuretic hormone secretion (SIADH). Other Weight gain or loss; perspiration, flushing; urinary frequency, nocturia; parotid swelling; drowsiness, dizziness, proneness to falling, weakness and fatigue, headache; fever; alopecia; elevated alkaline phosphatase. Withdrawal Symptoms Though not indicative of addiction, abrupt cessation of treatment after prolonged therapy may produce nausea, headache, and malaise.
Clinical Worsening and Suicide Risk Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide. There has been a long-standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (SSRIs and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with major depressive disorder (MDD) and other psychiatric disorders. Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients. There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs placebo), however, were relatively stable within age strata and across indications. These risk differences (drug-placebo difference in the number of cases of suicidality per 1000 patients treated) are provided in Table 1. Table 1 Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1000 Patients Treated Increases Compared to Placebo <18 14 additional cases 18-24 5 additional cases Decreases Compared to Placebo 25-64 1 fewer case ?65 6 fewer cases No suicides occurred in any of the pediatric trials. There were suicides in the adult trials, but the number was not sufficient to reach any conclusion about drug effect on suicide. It is unknown whether the suicidality risk extends to longer-term use, i.e., beyond several months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with depression that the use of antidepressants can delay the recurrence of depression. All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases. The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychiatric. Although a causal link between the emergence of such symptoms and either the worsening of depression and/or the emergence of suicidal impulses has not been established, there is concern that such symptoms may represent precursors to emerging suicidality. Consideration should be given to changing the therapeutic regimen, including possibly discontinuing the medication, in patients whose depression is persistently worse, or who are experiencing emergent suicidality or symptoms that might be precursors to worsening depression or suicidality, especially if these symptoms are severe, abrupt in onset, or were not part of the patient's presenting symptoms. Families and caregivers of patients being treated with antidepressants for major depressive disorder or other indications, both psychiatric and nonpsychiatric, should be alerted about the need to monitor patients for the emergence of agitation, irritability, unusual changes in behavior, and the other symptoms described above, as well as the emergence of suicidality, and to report such symptoms immediately to health care providers. Such monitoring should include daily observation by families and caregivers. Prescriptions for desipramine hydrochloride should be written for the smallest quantity of tablets consistent with good patient management, in order to reduce the risk of overdose. Screening Patients for Bipolar Disorder A major depressive episode may be the initial presentation of bipolar disorder. It is generally believed (though not established in controlled trials) that treating such an episode with an antidepressant alone may increase the likelihood of precipitation of a mixed/manic episode in patients at risk for bipolar disorder. Whether any of the symptoms described above represent such a conversion is unknown. However, prior to initiating treatment with an antidepressant, patients with depressive symptoms should be adequately screened to determine if they are at risk for bipolar disorder; such screening should include a detailed psychiatric history, including a family history of suicide, bipolar disorder, and depression. It should be noted that desipramine hydrochloride is not approved for use in treating bipolar depression. General Extreme caution should be used when this drug is given in the following situations: a. In patients with cardiovascular disease, because of the possibility of conduction defects, arrhythmias, tachycardias, strokes, and acute myocardial infarction. b. In patients who have a family history of sudden death, cardiac dysrhythmias, or cardiac conduction disturbances. c. In patients with a history of urinary retention or glaucoma, because of the anticholinergic properties of the drug. d. In patients with thyroid disease or those taking thyroid medication, because of the possibility of cardiovascular toxicity, including arrhythmias. e. In patients with a history of seizure disorder, because this drug has been shown to lower the seizure threshold. Seizures precede cardiac dysrhythmias and death in some patients. This drug is capable of blocking the antihypertensive effect of guanethidine and similarly acting compounds. The patient should be cautioned that this drug may impair the mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving a car or operating machinery. In patients who may use alcohol excessively, it should be borne in mind that the potentiation may increase the danger inherent in any suicide attempt or overdosage. Use in Pregnancy Safe use of desipramine hydrochloride during pregnancy and lactation has not been established; therefore, if it is to be given to pregnant patients, nursing mothers, or women of childbearing potential, the possible benefits must be weighed against the possible hazards to mother and child. Animal reproductive studies have been inconclusive. Geriatric Use Clinical studies of desipramine hydrochloride did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Lower doses are recommended for elderly patients. (See DOSAGE AND ADMINISTRATION .) The ratio of 2-hydroxydesipramine to desipramine may be increased in the elderly, most likely due to decreased renal elimination with aging. This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Desipramine hydrochloride use in the elderly has been associated with a proneness to falling as well as confusional states. (See ADVERSE REACTIONS .) --- BOXED WARNING: Suicidality and Antidepressant Drugs Antidepressants increased the risk compared to placebo of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults in short-term studies of major depressive disorder (MDD) and other psychiatric disorders. Anyone considering the use of desipramine hydrochloride tablets or any other antidepressant in a child, adolescent, or young adult must balance this risk with the clinical need. Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction in risk with antidepressants compared to placebo in adults aged 65 and older. Depression and certain other psychiatric disorders are themselves associated with increases in the risk of suicide. Patients of all ages who are started on antidepressant therapy should be monitored appropriately and observed closely for clinical worsening, suicidality, or unusual changes in behavior. Families and caregivers should be advised of the need for close observation and communication with the prescriber. Desipramine hydrochloride is not approved for use in pediatric patients. (See WARNINGS: Clinical Worsening and Suicide Risk , PRECAUTIONS: Information for Patients , and PRECAUTIONS: Pediatric Use .)
Drugs Metabolized by P450 2D6 The biochemical activity of the drug metabolizing isozyme cytochrome P450 2D6 (debrisoquin hydroxylase) is reduced in a subset of the Caucasian population (about 7% to 10% of Caucasians are so called "poor metabolizers"); reliable estimates of the prevalence of reduced P450 2D6 isozyme activity among Asian, African and other populations are not yet available. Poor metabolizers have higher than expected plasma concentrations of tricyclic antidepressants (TCAs) when given usual doses. Depending on the fraction of drug metabolized by P450 2D6, the increase in plasma concentration may be small, or quite large (8 fold increase in plasma AUC of the TCA). In addition, certain drugs inhibit the activity of this isozyme and make normal metabolizers resemble poor metabolizers. An individual who is stable on a given dose of TCA may become abruptly toxic when given one of these inhibiting drugs as concomitant therapy. The drugs that inhibit cytochrome P450 2D6 include some that are not metabolized by the enzyme (quinidine; cimetidine) and many that are substrates for P450 2D6 (many other antidepressants, phenothiazines, and the Type IC antiarrhythmics propafenone and flecainide). While all the selective serotonin reuptake inhibitors (SSRIs), e.g., fluoxetine, sertraline, and paroxetine, inhibit P450 2D6, they may vary in the extent of inhibition. The extent to which SSRI TCA interactions may pose clinical problems will depend on the degree of inhibition and the pharmacokinetics of the SSRI involved. Nevertheless, caution is indicated in the co-administration of TCAs with any of the SSRIs and also in switching from one class to the other. Of particular importance, sufficient time must elapse before initiating TCA treatment in a patient being withdrawn from fluoxetine, given the long half-life of the parent and active metabolite (at least 5 weeks may be necessary). Concomitant use of tricyclic antidepressants with drugs that can inhibit cytochrome P450 2D6 may require lower doses than usually prescribed for either the tricyclic antidepressant or the other drug. Furthermore, whenever one of these other drugs is withdrawn from co-therapy, an increased dose of tricyclic antidepressant may be required. It is desirable to monitor TCA plasma levels whenever a TCA is going to be co-administered with another drug known to be an inhibitor of P450 2D6. Close supervision and careful adjustment of dosage are required when this drug is given concomitantly with anticholinergic or sympathomimetic drugs. Patients should be warned that while taking this drug their response to alcoholic beverages may be exaggerated. If desipramine hydrochloride is to be combined with other psychotropic agents such as tranquilizers or sedative/hypnotics, careful consideration should be given to the pharmacology of the agents employed since the sedative effects of desipramine and benzodiazepines (e.g., chlordiazepoxide or diazepam) are additive. Both the sedative and anticholinergic effects of the major tranquilizers are also additive to those of desipramine.