

İHALE DÜNYASI
İHALE DÜNYASI


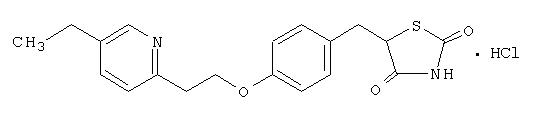
ACTOS (pioglitazone hydrochloride) is an oral antidiabetic medication. Pioglitazone [(±)-5-[[4-[2-(5-ethyl-2-pyridinyl) ethoxy] phenyl] methyl]-2,4-] thiazolidinedione monohydrochloride contains one asymmetric carbon, and the compound is synthesized and used as the racemic mixture. The two enantiomers of pioglitazone interconvert in vivo . No differences were found in the pharmacologic activity between the two enantiomers. The structural formula is as shown: Pioglitazone hydrochloride is an odorless white crystalline powder that has a molecular formula of C 19 H 20 N 2 O 3 S*HCl and a molecular weight of 392.90 daltons. It is soluble in N,N -dimethylformamide, slightly soluble in anhydrous ethanol, very slightly soluble in acetone and acetonitrile, practically insoluble in water, and insoluble in ether. ACTOS is available as a tablet for oral administration containing 15 mg, 30 mg, or 45 mg of pioglitazone (as the base) formulated with the following excipients: lactose monohydrate NF, hydroxypropylcellulose NF, carboxymethylcellulose calcium NF, and magnesium stearate NF. Chemical Structure Figure 1
ACTOS is a thiazolidinedione and an agonist for peroxisome proliferator-activated receptor (PPAR) gamma indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus in multiple clinical settings. ( 1.1 , 14 ) Important Limitation of Use: Not for treatment of type 1 diabetes or diabetic ketoacidosis. ( 1.2 ) 1.1 Monotherapy and Combination Therapy ACTOS is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus in multiple clinical settings [see Clinical Studies (14) ] . 1.2 Important Limitation of Use ACTOS exerts its antihyperglycemic effect only in the presence of endogenous insulin. ACTOS should not be used to treat type 1 diabetes or diabetic ketoacidosis, as it would not be effective in these settings. Use caution in patients with liver disease [see Warnings and Precautions (5.3) ] .
Initiate ACTOS at 15 mg or 30 mg once daily. Limit initial dose to 15 mg once daily in patients with NYHA Class I or II heart failure. ( 2.1 ) If there is inadequate glycemic control, the dose can be increased in 15 mg increments up to a maximum of 45 mg once daily. ( 2.1 ) The maximum recommended dose of ACTOS is 15 mg once daily in patients taking strong CYP2C8 inhibitors (e.g., gemfibrozil). ( 2.3 , 7.1 ) Obtain liver tests before starting ACTOS. If abnormal, use caution when treating with ACTOS, investigate the probable cause, treat (if possible) and follow appropriately. Monitoring liver tests while on ACTOS is not recommended in patients without liver disease. ( 5.3 ) 2.1 Recommendations for all patients ACTOS should be taken once daily and can be taken without regard to meals. The recommended starting dose for patients without congestive heart failure is 15 mg or 30 mg once daily. The recommended starting dose for patients with congestive heart failure (NYHA Class I or II) is 15 mg once daily. The dose can be titrated in increments of 15 mg up to a maximum of 45 mg once daily based on glycemic response as determined by HbA1c. After initiation of ACTOS or with dose increase, monitor patients carefully for adverse reactions related to fluid retention such as weight gain, edema, and signs and symptoms of congestive heart failure [see Boxed Warning and Warnings and Precautions (5.2) ] . Liver tests (serum alanine and aspartate aminotransferases, alkaline phosphatase, and total bilirubin) should be obtained prior to initiating ACTOS. Routine periodic monitoring of liver tests during treatment with ACTOS is not recommended in patients without liver disease. Patients who have liver test abnormalities prior to initiation of ACTOS or who are found to have abnormal liver tests while taking ACTOS should be managed as described under Warnings and Precautions [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.3) ] . 2.2 Concomitant use with an insulin secretagogue or insulin If hypoglycemia occurs in a patient co-administered ACTOS and an insulin secretagogue (e.g., sulfonylurea), the dose of the insulin secretagogue should be reduced. If hypoglycemia occurs in a patient co-administered ACTOS and insulin, the dose of insulin should be decreased by 10% to 25%. Further adjustments to the insulin dose should be individualized based on glycemic response. 2.3 Coadministration with strong CYP2C8 inhibitors Coadministration of ACTOS and gemfibrozil, a strong CYP2C8 inhibitor, increases pioglitazone exposure approximately 3-fold. Therefore, the maximum recommended dose of ACTOS is 15 mg daily when used in combination with gemfibrozil or other strong CYP2C8 inhibitors [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ].
Do not initiate in patients with NYHA Class III or IV heart failure [see Boxed Warning ] . Do not use in patients with a history of a serious hypersensitivity reaction to ACTOS or any of its ingredients. Do not initiate ACTOS in patients with established NYHA Class III or IV heart failure. ( 4 ) Do not use in patients with a history of a serious hypersensitivity reaction to ACTOS or its ingredients. ( 4 )
The following serious adverse reactions are discussed elsewhere in the labeling: Congestive heart failure [see Boxed Warning and Warnings and Precautions (5.1) ] Edema [see Warnings and Precautions (5.2) ] Fractures [see Warnings and Precautions (5.4) ] Most common adverse reactions (? 5% and at a rate higher than with placebo) include upper respiratory tract infection, headache, sinusitis, myalgia, and pharyngitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Takeda Pharmaceuticals at 1-877-825-3327 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. 6.1 Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Over 8500 patients with type 2 diabetes have been treated with ACTOS in randomized, double-blind, controlled clinical trials, including 2605 patients with type 2 diabetes and macrovascular disease treated with ACTOS in the PROactive clinical trial. In these trials, over 6000 patients have been treated with ACTOS for 6 months or longer, over 4500 patients have been treated with ACTOS for one year or longer, and over 3000 patients have been treated with ACTOS for at least 2 years. In six pooled 16 to 26-week placebo-controlled monotherapy and 16 to 24-week add-on combination therapy trials, the incidence of withdrawals due to adverse events was 4.5% for patients treated with ACTOS and 5.8% for comparator-treated patients. The most common adverse events leading to withdrawal were related to inadequate glycemic control, although the incidence of these events was lower (1.5%) with ACTOS than with placebo (3.0%). In the PROactive trial, the incidence of withdrawals due to adverse events was 9.0% for patients treated with ACTOS and 7.7% for placebo-treated patients. Congestive heart failure was the most common serious adverse event leading to withdrawal occurring in 1.3% of patients treated with ACTOS and 0.6% of patients treated with placebo. Common Adverse Events: 16 to 26-Week Monotherapy Trials A summary of the incidence and type of common adverse events reported in three pooled 16 to 26-week placebo-controlled monotherapy trials of ACTOS is provided in Table 1. Terms that are reported represent those that occurred at an incidence of >5% and more commonly in patients treated with ACTOS than in patients who received placebo. None of these adverse events were related to ACTOS dose. Table 1: Three Pooled 16 to 26 Week Placebo-Controlled Clinical Trials of ACTOS Monotherapy: Adverse Events Reported at an Incidence > 5% and More Commonly in Patients Treated with ACTOS than in Patients Treated with Placebo % of Patients Placebo N=259 ACTOS N=606 Upper Respiratory Tract Infection 8.5 13.2 Headache 6.9 9.1 Sinusitis 4.6 6.3 Myalgia 2.7 5.4 Pharyngitis 0.8 5.1 Common Adverse Events: 16 to 24-Week Add-on Combination Therapy Trials A summary of the overall incidence and types of common adverse events reported in trials of ACTOS add-on to sulfonylurea is provided in Table 2. Terms that are reported represent those that occurred at an incidence of >5% and more commonly with the highest tested dose of ACTOS. Table 2: 16 to 24 Week Clinical Trials of ACTOS Add-on to Sulfonylurea Note: The preferred terms of edema peripheral, generalized edema, pitting edema and fluid retention were combined to form the aggregate term of "edema." 16-Week Placebo-Controlled Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS 30 mg + Sulfonylurea than in Patients Treated with Placebo + Sulfonylurea % of Patients Placebo + Sulfonylurea N=187 ACTOS 15 mg + Sulfonylurea N=184 ACTOS 30 mg + Sulfonylurea N=189 Edema 2.1 1.6 12.7 Headache 3.7 4.3 5.3 Flatulence 0.5 2.7 6.3 Weight Increased 0 2.7 5.3 24-Week Non-Controlled Double-Blind Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS 45 mg + Sulfonylurea than in Patients Treated with ACTOS 30 mg + Sulfonylurea % of Patients ACTOS 30 mg + Sulfonylurea N=351 ACTOS 45 mg + Sulfonylurea N=351 Hypoglycemia 13.4 15.7 Edema 10.5 23.1 Upper Respiratory Tract Infection 12.3 14.8 Weight Increased 9.1 13.4 Urinary Tract Infection 5.7 6.8 A summary of the overall incidence and types of common adverse events reported in trials of ACTOS add-on to metformin is provided in Table 3. Terms that are reported represent those that occurred at an incidence of >5% and more commonly with the highest tested dose of ACTOS. Table 3: 16 to 24 Week Clinical Trials of ACTOS Add-on to Metformin Note: The preferred terms of edema peripheral, generalized edema, pitting edema and fluid retention were combined to form the aggregate term of "edema." 16-Week Placebo-Controlled Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS + Metformin than in Patients Treated with Placebo + Metformin % of Patients Placebo + Metformin N=160 ACTOS 30 mg + Metformin N=168 Edema 2.5 6.0 Headache 1.9 6.0 24-Week Non-Controlled Double-Blind Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS 45 mg + Metformin than in Patients Treated with ACTOS 30 mg + Metformin % of Patients ACTOS 30 mg + Metformin N=411 ACTOS 45 mg + Metformin N=416 Upper Respiratory Tract Infection 12.4 13.5 Edema 5.8 13.9 Headache 5.4 5.8 Weight Increased 2.9 6.7 Table 4 summarizes the incidence and types of common adverse events reported in trials of ACTOS add-on to insulin. Terms that are reported represent those that occurred at an incidence of >5% and more commonly with the highest tested dose of ACTOS. Table 4: 16 to 24 Week Clinical Trials of ACTOS Add-on to Insulin Note: The preferred terms of edema peripheral, generalized edema, pitting edema and fluid retention were combined to form the aggregate term of "edema." 16-Week Placebo-Controlled Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS 30 mg + Insulin than in Patients Treated with Placebo + Insulin % of Patients Placebo +Insulin N=187 ACTOS 15 mg + Insulin N=191 ACTOS 30 mg + Insulin N=188 Hypoglycemia 4.8 7.9 15.4 Edema 7.0 12.6 17.6 Upper Respiratory Tract Infection 9.6 8.4 14.9 Headache 3.2 3.1 6.9 Weight Increased 0.5 5.2 6.4 Back Pain 4.3 2.1 5.3 Dizziness 3.7 2.6 5.3 Flatulence 1.6 3.7 5.3 24-Week Non-Controlled Double-Blind Trial Adverse Events Reported in > 5% of Patients and More Commonly in Patients Treated with ACTOS 45 mg + Insulin than in Patients Treated with ACTOS 30 mg + Insulin % of Patients ACTOS 30 mg + Insulin N=345 ACTOS 45 mg + Insulin N=345 Hypoglycemia 43.5 47.8 Edema 22.0 26.1 Weight Increased 7.2 13.9 Urinary Tract Infection 4.9 8.7 Diarrhea 5.5 5.8 Back Pain 3.8 6.4 Blood Creatine Phosphokinase Increased 4.6 5.5 Sinusitis 4.6 5.5 Hypertension 4.1 5.5 A summary of the overall incidence and types of common adverse events reported in the PROactive trial is provided in Table 5. Terms that are reported represent those that occurred at an incidence of >5% and more commonly in patients treated with ACTOS than in patients who received placebo. Table 5: PROactive Trial: Incidence and Types of Adverse Events Reported in > 5% of Patients Treated with ACTOS and More Commonly than Placebo % of Patients Placebo N=2633 ACTOS N=2605 Mean duration of patient follow-up was 34.5 months. Hypoglycemia 18.8 27.3 Edema 15.3 26.7 Cardiac Failure 6.1 8.1 Pain in Extremity 5.7 6.4 Back Pain 5.1 5.5 Chest Pain 5.0 5.1 Congestive Heart Failure : A summary of the incidence of adverse events related to congestive heart failure is provided in Table 6 for the 16 to 24-week add-on to sulfonylurea trials, for the 16 to 24-week add-on to insulin trials, and for the 16 to 24-week add-on to metformin trials. None of the events were fatal. Table 6: Treatment -Emergent Adverse Events of Congestive Heart Failure (CHF) Patients Treated with ACTOS or Placebo Added on to a Sulfonylurea Number (%) of Patients Placebo-Controlled Trial (16 weeks) Non-Controlled Double Blind Trial (24 weeks) Placebo + Sulfonylurea N=187 ACTOS 15 mg + Sulfonylurea N=184 ACTOS 30 mg + Sulfonylurea N=189 ACTOS 30 mg + Sulfonylurea N=351 ACTOS 45 mg + Sulfonylurea N=351 At least one congestive heart failure event 2 (1.1%) 0 0 1 (0.3%) 6 (1.7%) Hospitalized 2 (1.1%) 0 0 0 2 (0.6%) Patients Treated with ACTOS or Placebo Added on to Insulin Number (%) of Patients Placebo-Controlled Trial (16 weeks) Non-Controlled Double Blind Trial (24 weeks) Placebo + Insulin N=187 ACTOS 15 mg + Insulin N=191 ACTOS 30 mg + Insulin N=188 ACTOS 30 mg + Insulin N=345 ACTOS 45 mg + Insulin N=345 At least one congestive heart failure event 0 2 (1.0%) 2 (1.1%) 3 (0.9%) 5 (1.4%) Hospitalized 0 2 (1.0%) 1 (0.5%) 1 (0.3%) 3 (0.9%) Patients Treated with ACTOS or Placebo Added on to Metformin Number (%) of Patients Placebo-Controlled Trial (16 weeks) Non-Controlled Double Blind Trial (24 weeks) Placebo + Metformin N=160 ACTOS 30 mg + Metformin N=168 ACTOS 30 mg + Metformin N=411 ACTOS 45 mg + Metformin N=416 At least one congestive heart failure event 0 1 (0.6%) 0 1 (0.2%) Hospitalized 0 1 (0.6%) 0 1 (0.2%) Patients with type 2 diabetes and NYHA class II or early class III congestive heart failure were randomized to receive 24 weeks of double-blind treatment with either ACTOS at daily doses of 30 mg to 45 mg (n=262) or glyburide at daily doses of 10 mg to 15 mg (n=256). A summary of the incidence of adverse events related to congestive heart failure reported in this study is provided in Table 7. Table 7: Treatment -Emergent Adverse Events of Congestive Heart Failure (CHF) in Patients with NYHA Class II or III Congestive Heart Failure Treated with ACTOS or Glyburide Number (%) of Subjects ACTOS N=262 Glyburide N=256 Death due to cardiovascular causes (adjudicated) 5 (1.9%) 6 (2.3%) Overnight hospitalization for worsening CHF (adjudicated) 26 (9.9%) 12 (4.7%) Emergency room visit for CHF (adjudicated) 4 (1.5%) 3 (1.2%) Patients experiencing CHF progression during study 35 (13.4%) 21 (8.2%) Congestive heart failure events leading to hospitalization that occurred during the PROactive trial are summarized in Table 8. Table 8: Treatment -Emergent Adverse Events of Congestive Heart Failure (CHF) in PROactive Trial Number (%) of Patients Placebo N=2633 ACTOS N=2605 At least one hospitalized congestive heart failure event 108 (4.1%) 149 (5.7%) Fatal 22 (0.8%) 25 (1.0%) Hospitalized, non-fatal 86 (3.3%) 124 (4.7%) Cardiovascular Safety: In the PROactive trial, 5238 patients with type 2 diabetes and a history of macrovascular disease were randomized to ACTOS (N=2605), force-titrated up to 45 mg daily or placebo (N=2633) in addition to standard of care. Almost all patients (95%) were receiving cardiovascular medications (beta blockers, ACE inhibitors, angiotensin II receptor blockers, calcium channel blockers, nitrates, diuretics, aspirin, statins and fibrates). At baseline, patients had a mean age of 62 years, mean duration of diabetes of 9.5 years, and mean HbA1c of 8.1%. Mean duration of follow-up was 34.5 months. The primary objective of this trial was to examine the effect of ACTOS on mortality and macrovascular morbidity in patients with type 2 diabetes mellitus who were at high risk for macrovascular events. The primary efficacy variable was the time to the first occurrence of any event in a cardiovascular composite endpoint that included all-cause mortality, non-fatal myocardial infarction (MI) including silent MI, stroke, acute coronary syndrome, cardiac intervention including coronary artery bypass grafting or percutaneous intervention, major leg amputation above the ankle, and bypass surgery or revascularization in the leg. A total of 514 (19.7%) patients treated with ACTOS and 572 (21.7%) placebo-treated patients experienced at least one event from the primary composite endpoint (hazard ratio 0.90; 95% Confidence Interval: 0.80, 1.02; p=0.10). Although there was no statistically significant difference between ACTOS and placebo for the 3-year incidence of a first event within this composite, there was no increase in mortality or in total macrovascular events with ACTOS. The number of first occurrences and total individual events contributing to the primary composite endpoint is shown in Table 9. Table 9: PROactive: Number of First and Total Events for Each Component within the Cardiovascular Composite Endpoint Cardiovascular Events Placebo N=2633 ACTOS N=2605 First Events n (%) Total events n First Events n (%) Total events n CABG = coronary artery bypass grafting; PCI = percutaneous intervention Any event 572 (21.7) 900 514 (19.7) 803 All-cause mortality 122 (4.6) 186 110 (4.2) 177 Non-fatal myocardial infarction (MI) 118 (4.5) 157 105 (4.0) 131 Stroke 96 (3.6) 119 76 (2.9) 92 Acute coronary syndrome 63 (2.4) 78 42 (1.6) 65 Cardiac intervention (CABG/PCI) 101 (3.8) 240 101 (3.9) 195 Major leg amputation 15 (0.6) 28 9 (0.3) 28 Leg revascularization 57 (2.2) 92 71 (2.7) 115 Weight Gain : Dose-related weight gain occurs when ACTOS is used alone or in combination with other anti-diabetic medications. The mechanism of weight gain is unclear but probably involves a combination of fluid retention and fat accumulation. Tables 10 and 11 summarize the changes in body weight with ACTOS and placebo in the 16 to 26-week randomized, double-blind monotherapy and 16 to 24-week combination add-on therapy trials and in the PROactive trial. Table 10: Weight Changes (kg) from Baseline during Randomized, Double-Blind Clinical Trials Control Group (Placebo) ACTOS 15 mg ACTOS 30 mg ACTOS 45 mg Median (25 th /75 th percentile) Median (25 th /75 th percentile) Median (25 th /75 th percentile) Median (25 th /75 th percentile) Monotherapy (16 to 26 weeks) -1.4 (-2.7/0.0) N=256 0.9 (-0.5/3.4) N=79 1.0 (-0.9/3.4) N=188 2.6 (0.2/5.4) N=79 Combination Therapy (16 to 24 weeks) Sulfonylurea -0.5 (-1.8/0.7) N=187 2.0 (0.2/3.2) N=183 3.1 (1.1/5.4) N=528 4.1 (1.8/7.3) N=333 Metformin -1.4 (-3.2/0.3) N=160 N/A 0.9 (-1.3/3.2) N=567 1.8 (-0.9/5.0) N=407 Insulin 0.2 (-1.4/1.4) N=182 2.3 (0.5/4.3) N=190 3.3 (0.9/6.3) N=522 4.1 (1.4/6.8) N=338 Table 11: Median Change in Body Weight in Patients Treated with ACTOS Versus Patients Treated with Placebo During the Double-Blind Treatment Period in the PROactive Trial Placebo ACTOS Median (25 th /75 th percentile) Median (25 th /75 th percentile) Note: median exposure for both ACTOS and Placebo was 2.7 years. Change from Baseline to Final Visit (kg) -0.5 (-3.3, 2.0) N=2581 +3.6 (0.0, 7.5) N=2560 Edema : Edema induced from taking ACTOS is reversible when ACTOS is discontinued. The edema usually does not require hospitalization unless there is coexisting congestive heart failure. A summary of the frequency and types of edema adverse events occurring in clinical investigations of ACTOS is provided in Table 12. Table 12: Adverse Events of Edema in Patients Treated with ACTOS Number (%) of Patients Placebo ACTOS 15 mg ACTOS 30 mg ACTOS 45 mg Note: The preferred terms of edema peripheral, generalized edema, pitting edema and fluid retention were combined to form the aggregate term of "edema." Monotherapy (16 to 26 weeks) 3 (1.2%) N=259 2(2.5%) N= 81 13 (4.7%) N= 275 11 (6.5%) N=169 Combined Therapy (16 to 24 weeks) Sulfonylurea 4 (2.1%) N=187 3(1.6%) N=184 61 (11.3%) N=540 81 (23.1%) N=351 Metformin 4 (2.5%) N=160 N/A 34 (5.9%) N=579 58 (13.9%) N=416 Insulin 13 (7.0%) N=187 24(12.6%) N=191 109(20.5%) N=533 90 (26.1%) N=345 Table 13: Adverse Events of Edema in Patients in the PROactive Trial Number (%) of Patients Placebo N=2633 ACTOS N=2605 Note: The preferred terms of edema peripheral, generalized edema, pitting edema and fluid retention were combined to form the aggregate term of "edema." 419 (15.9%) 712 (27.3%) Hepatic Effects : There has been no evidence of ACTOS-induced hepatotoxicity in the ACTOS controlled clinical trial database to date. One randomized, double-blind, 3-year trial comparing ACTOS to glyburide as add-on to metformin and insulin therapy was specifically designed to evaluate the incidence of serum ALT elevation to greater than 3 times the upper limit of the reference range, measured every 8 weeks for the first 48 weeks of the trial then every 12 weeks thereafter. A total of 3/1051 (0.3%) patients treated with ACTOS and 9/1046 (0.9%) patients treated with glyburide developed ALT values >3 times the upper limit of the reference range. None of the patients treated with ACTOS in the ACTOS controlled clinical trial database to date have had a serum ALT > 3 times the upper limit of the reference range and a corresponding total bilirubin >2 times the upper limit of the reference range, a combination predictive of the potential for severe drug-induced liver injury. Hypoglycemia : In the ACTOS clinical trials, adverse events of hypoglycemia were reported based on clinical judgment of the investigators and did not require confirmation with fingerstick glucose testing. In the 16-week add-on to sulfonylurea trial, the incidence of reported hypoglycemia was 3.7% with ACTOS 30 mg and 0.5% with placebo. In the 16-week add-on to insulin trial, the incidence of reported hypoglycemia was 7.9% with ACTOS 15 mg, 15.4% with ACTOS 30 mg, and 4.8% with placebo. The incidence of reported hypoglycemia was higher with ACTOS 45 mg compared to ACTOS 30 mg in both the 24-week add-on to sulfonylurea trial (15.7% vs. 13.4%) and in the 24-week add-on to insulin trial (47.8% vs. 43.5%). Three patients in these four trials were hospitalized due to hypoglycemia. All three patients were receiving ACTOS 30 mg (0.9%) in the 24-week add-on to insulin trial. An additional 14 patients reported severe hypoglycemia (defined as causing considerable interference with patient's usual activities) that did not require hospitalization. These patients were receiving ACTOS 45 mg in combination with sulfonylurea (n=2) or ACTOS 30 mg or 45 mg in combination with insulin (n=12). Urinary Bladder Tumors : Tumors were observed in the urinary bladder of male rats in the two-year carcinogenicity study [see Nonclinical Toxicology (13.1 )] . In two 3-year trials in which ACTOS was compared to placebo or glyburide, there were 16/3656 (0.44%) reports of bladder cancer in patients taking ACTOS compared to 5/3679 (0.14%) in patients not taking ACTOS. After excluding patients in whom exposure to study drug was less than one year at the time of diagnosis of bladder cancer, there were six (0.16%) cases on ACTOS and two (0.05%) cases on placebo. There are too few events of bladder cancer to establish causality. 6.2 Laboratory Abnormalities Hematologic Effects : ACTOS may cause decreases in hemoglobin and hematocrit. In placebo-controlled monotherapy trials, mean hemoglobin values declined by 2% to 4% in patients treated with ACTOS compared with a mean change in hemoglobin of -1% to +1% in placebo-treated patients. These changes primarily occurred within the first 4 to 12 weeks of therapy and remained relatively constant thereafter. These changes may be related to increased plasma volume associated with ACTOS therapy and are not likely to be associated with any clinically significant hematologic effects. Creatine Phosphokinase : During protocol-specified measurement of serum creatine phosphokinase (CPK) in ACTOS clinical trials, an isolated elevation in CPK to greater than 10 times the upper limit of the reference range was noted in 9 (0.2%) patients treated with ACTOS (values of 2150 to 11400 IU/L) and in no comparator-treated patients. Six of these nine patients continued to receive ACTOS, two patients were noted to have the CPK elevation on the last day of dosing and one patient discontinued ACTOS due to the elevation. These elevations resolved without any apparent clinical sequelae. The relationship of these events to ACTOS therapy is unknown. 6.3 Postmarketing Experience The following adverse reactions have been identified during post-approval use of ACTOS. Because these reactions are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. New onset or worsening diabetic macular edema with decreased visual acuity [see Warnings and Precautions (5.2) ] . Fatal and non-fatal hepatic failure [see Warnings and Precautions (5.3) ] . Postmarketing reports of congestive heart failure have been reported in patients treated with ACTOS, both with and without previously known heart disease and both with and without concomitant insulin administration. In postmarketing experience, there have been reports of unusually rapid increases in weight and increases in excess of that generally observed in clinical trials. Patients who experience such increases should be assessed for fluid accumulation and volume-related events such as excessive edema and congestive heart failure [see Boxed Warning and Warnings and Precautions (5.1) ] .
Congestive heart failure: Fluid retention may occur and can exacerbate or lead to congestive heart failure. Combination use with insulin and use in congestive heart failure NYHA Class I and II may increase risk. Monitor patients for signs and symptoms. ( 5.1 ) Edema: Dose-related edema may occur. ( 5.2 ) Hepatic effects: Postmarketing reports of hepatic failure, sometimes fatal. Causality cannot be excluded. If liver injury is detected, promptly interrupt ACTOS and assess patient for probable cause, then treat cause if possible, to resolution or stabilization. Do not restart ACTOS if liver injury is confirmed and no alternate etiology can be found. ( 5.3 ) Fractures: Increased incidence in female patients. Apply current standards of care for assessing and maintaining bone health. ( 5.4 ) Bladder cancer: Preclinical and clinical trial data, and results from an observational study suggest an increased risk of bladder cancer in pioglitazone users. The observational data further suggest that the risk increases with duration of use. Do not use in patients with active bladder cancer. Use caution when using in patients with a prior history of bladder cancer ( 5.5 ) Hypoglycemia: When used with insulin or an insulin secretagogue, a lower dose of the insulin or insulin secretagogue may be needed to reduce the risk of hypoglycemia. ( 5.6 ) Macular edema: Postmarketing reports. Recommend regular eye exams in all patients with diabetes according to current standards of care with prompt evaluation for acute visual changes. ( 5.7 ) Macrovascular outcomes: There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with ACTOS or any other anti-diabetic drug. ( 5.9 ) 5.1 Congestive Heart Failure ACTOS, like other thiazolidinediones, can cause dose-related fluid retention when used alone or in combination with other antidiabetic medications and is most common when ACTOS is used in combination with insulin. Fluid retention may lead to or exacerbate congestive heart failure. Patients should be observed for signs and symptoms of congestive heart failure. If congestive heart failure develops, it should be managed according to current standards of care and discontinuation or dose reduction of ACTOS must be considered [see Boxed Warning , Contraindications (4) , and Adverse Reactions (6.1) ] . 5.2 Edema In controlled clinical trials, edema was reported more frequently in patients treated with ACTOS than in placebo-treated patients and is dose-related [see Adverse Reactions (6.1) ] . In postmarketing experience, reports of new onset or worsening edema have been received. ACTOS should be used with caution in patients with edema. Because thiazolidinediones, including ACTOS, can cause fluid retention, which can exacerbate or lead to congestive heart failure, ACTOS should be used with caution in patients at risk for congestive heart failure. Patients treated with ACTOS should be monitored for signs and symptoms of congestive heart failure [see Boxed Warning , Warnings and Precautions (5.1) and Patient Counseling Information (17.1) ] . 5.3 Hepatic Effects There have been postmarketing reports of fatal and non-fatal hepatic failure in patients taking ACTOS, although the reports contain insufficient information necessary to establish the probable cause. There has been no evidence of drug-induced hepatotoxicity in the ACTOS controlled clinical trial database to date [see Adverse Reactions (6.1) ] . Patients with type 2 diabetes may have fatty liver disease or cardiac disease with episodic congestive heart failure, both of which may cause liver test abnormalities, and they may also have other forms of liver disease, many of which can be treated or managed. Therefore, obtaining a liver test panel (serum alanine aminotransferase [ALT], aspartate aminotransferase [AST], alkaline phosphatase, and total bilirubin) and assessing the patient is recommended before initiating ACTOS therapy. In patients with abnormal liver tests, ACTOS should be initiated with caution. Measure liver tests promptly in patients who report symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice. In this clinical context, if the patient is found to have abnormal liver tests (ALT greater than 3 times the upper limit of the reference range), ACTOS treatment should be interrupted and investigation done to establish the probable cause. ACTOS should not be restarted in these patients without another explanation for the liver test abnormalities. Patients who have serum ALT greater than three times the reference range with serum total bilirubin greater than two times the reference range without alternative etiologies are at risk for severe drug-induced liver injury, and should not be restarted on ACTOS. For patients with lesser elevations of serum ALT or bilirubin and with an alternate probable cause, treatment with ACTOS can be used with caution. 5.4 Fractures In PROactive (the Prospective Pioglitazone Clinical Trial in Macrovascular Events), 5238 patients with type 2 diabetes and a history of macrovascular disease were randomized to ACTOS (N=2605), force-titrated up to 45 mg daily or placebo (N=2633) in addition to standard of care. During a mean follow-up of 34.5 months, the incidence of bone fracture in females was 5.1% (44/870) for ACTOS versus 2.5% (23/905) for placebo. This difference was noted after the first year of treatment and persisted during the course of the study. The majority of fractures observed in female patients were nonvertebral fractures including lower limb and distal upper limb. No increase in the incidence of fracture was observed in men treated with ACTOS (1.7%) versus placebo (2.1%). The risk of fracture should be considered in the care of patients, especially female patients, treated with ACTOS and attention should be given to assessing and maintaining bone health according to current standards of care. 5.5 Urinary Bladder Tumors Tumors were observed in the urinary bladder of male rats in the two-year carcinogenicity study [see Nonclinical Toxicology (13.1) ]. In two 3-year trials in which ACTOS was compared to placebo or glyburide, there were 16/3656 (0.44%) reports of bladder cancer in patients taking ACTOS compared to 5/3679 (0.14%) in patients not taking ACTOS. After excluding patients in whom exposure to study drug was less than one year at the time of diagnosis of bladder cancer, there were six (0.16%) cases on ACTOS and two (0.05%) cases on placebo. A five-year interim report of an ongoing 10-year observational cohort study found a non-significant increase in the risk for bladder cancer in subjects ever exposed to ACTOS, compared to subjects never exposed to ACTOS (HR 1.2 [95% CI 0.9 - 1.5]). Compared to never exposure, a duration of ACTOS therapy longer than 12 months was associated with an increase in risk (HR 1.4 [95% CI 0.9 - 2.1]), which reached statistical significance after more than 24 months of ACTOS use (HR 1.4 [95% CI 1.03 - 2.0]). Interim results from this study suggested that taking ACTOS longer than 12 months increased the relative risk of developing bladder cancer in any given year by 40% which equates to an absolute increase of 3 cases in 10,000 (from approximately 7 in 10,000 [without ACTOS] to approximately 10 in 10,000 [with ACTOS]). There are insufficient data to determine whether pioglitazone is a tumor promoter for urinary bladder tumors. Consequently, ACTOS should not be used in patients with active bladder cancer and the benefits of glycemic control versus unknown risks for cancer recurrence with ACTOS should be considered in patients with a prior history of bladder cancer. 5.6 Hypoglycemia Patients receiving ACTOS in combination with insulin or other anti-diabetic medications (particularly insulin secretagogues such as sulfonylureas) may be at risk for hypoglycemia. A reduction in the dose of the concomitant anti-diabetic medication may be necessary to reduce the risk of hypoglycemia [see Dosage and Administration (2.2) ]. 5.7 Macular Edema Macular edema has been reported in postmarketing experience in diabetic patients who were taking ACTOS or another thiazolidinedione. Some patients presented with blurred vision or decreased visual acuity, but others were diagnosed on routine ophthalmologic examination. Most patients had peripheral edema at the time macular edema was diagnosed. Some patients had improvement in their macular edema after discontinuation of the thiazolidinedione. Patients with diabetes should have regular eye exams by an ophthalmologist according to current standards of care. Patients with diabetes who report any visual symptoms should be promptly referred to an ophthalmologist, regardless of the patient's underlying medications or other physical findings [see Adverse Reactions (6.1) ] . 5.8 Ovulation Therapy with ACTOS, like other thiazolidinediones, may result in ovulation in some premenopausal anovulatory women. As a result, these patients may be at an increased risk for pregnancy while taking ACTOS [see Use in Specific Populations (8.1) ] . This effect has not been investigated in clinical trials, so the frequency of this occurrence is not known. Adequate contraception in all premenopausal women treated with ACTOS is recommended. 5.9 Macrovascular Outcomes There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with ACTOS or any other anti-diabetic drug. --- BOXED WARNING: WARNING: CONGESTIVE HEART FAILURE Thiazolidinediones, including ACTOS, cause or exacerbate congestive heart failure in some patients [see Warnings and Precautions (5.1) ] . After initiation of ACTOS, and after dose increases, monitor patients carefully for signs and symptoms of heart failure (e.g., excessive, rapid weight gain, dyspnea, and/or edema). If heart failure develops, it should be managed according to current standards of care and discontinuation or dose reduction of ACTOS must be considered. ACTOS is not recommended in patients with symptomatic heart failure. Initiation of ACTOS in patients with established New York Heart Association (NYHA) Class III or IV heart failure is contraindicated [see Contraindications (4) and Warnings and Precautions (5.1) ] . WARNING: CONGESTIVE HEART FAILURE See full prescribing information for complete boxed warning. Thiazolidinediones, including ACTOS, cause or exacerbate congestive heart failure in some patients. ( 5.1 ) After initiation of ACTOS, and after dose increases, monitor patients carefully for signs and symptoms of heart failure (e.g., excessive, rapid weight gain, dyspnea, and/or edema). If heart failure develops, it should be managed according to current standards of care and discontinuation or dose reduction of ACTOS must be considered. ( 5.1 ) ACTOS is not recommended in patients with symptomatic heart failure. Initiation of ACTOS in patients with established New York Heart Association (NYHA) Class III or IV heart failure is contraindicated. ( 4 , 5.1 )
Strong CYP2C8 inhibitors (e.g., gemfibrozil) increase pioglitazone concentrations. Limit ACTOS dose to 15 mg daily. ( 2.3 , 7.1 ) CYP2C8 inducers (e.g., rifampin) may decrease pioglitazone concentrations. ( 7.2 ) 7.1 Strong CYP2C8 Inhibitors An inhibitor of CYP2C8 (e.g., gemfibrozil) significantly increases the exposure (area under the serum concentration-time curve or AUC) and half-life of pioglitazone. Therefore, the maximum recommended dose of ACTOS is 15 mg daily if used in combination with gemfibrozil or other strong CYP2C8 inhibitors [see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ]. 7.2 CYP2C8 Inducers An inducer of CYP2C8 (e.g., rifampin) may significantly decrease the exposure (AUC) of pioglitazone. Therefore, if an inducer of CYP2C8 is started or stopped during treatment with ACTOS, changes in diabetes treatment may be needed based on clinical response without exceeding the maximum recommended daily dose of 45 mg for ACTOS [see Clinical Pharmacology (12.3) ] .